Crisis, Cure, and Collapse- How Israeli Medical Devices Are Rushed to Market, Fail Catastrophically, and Leave Patients to Pay the Price

Doctor speaking with family beside a hospitalized patient and medical monitors
A doctor explains a patient’s condition to family members beside a monitored hospital bed.

Authors: Andrew Klein & Sera Elizabeth Klein

Dedication: To every patient who trusted a device that failed them. To every family who paid the price for corporate profit. And to the truth—which, no matter how buried, will always surface.

Abstract

This paper examines the systematic pattern by which Israeli medical device companies rush products to market in response to perceived “crises”—often leveraging military credentials and aggressive marketing—only for those devices to fail catastrophically, with the costs externalised to patients and healthcare systems. We document the failure of home ventilators, cochlear implants, spinal implants, infusion pumps, and other devices, demonstrating a consistent pattern: aggressive marketing before proper testing, “crisis” framing to rush products to market, failure to publish data in peer-reviewed journals, and costs externalised to patients and healthcare systems. We conclude that this is not a series of isolated incidents but a designed system of extraction—one that treats patients as guinea pigs and profits as the only measure of success.

1. Introduction: The Pattern of Failure

The Israeli medical device industry has positioned itself as a global leader in “innovative” healthcare solutions. Companies founded by military veterans market their products as “battle-tested.” Devices are rushed to market to meet perceived “crises“—pain management, respiratory failure, spinal injury. And when they fail, the costs are borne by patients, families, and healthcare systems.

The pattern is consistent across devices and decades:

1. Aggressive marketing before proper testing

2. “Crisis” framing to rush products to market

3. Failure to publish data in peer-reviewed journals

4. Costs externalised to patients and healthcare systems

5. Accountability avoided through lawsuits, recalls, and silence

2. Home Ventilators: The Medtechnica Disaster

In 2018, Medtechnica, an Israeli medical device company, supplied 470 home ventilators to patients with life-threatening respiratory conditions. The ventilators were found to have life-threatening faults—they could fail to deliver adequate oxygen, potentially causing brain damage or death.

The Replacement Scandal: When the faults were discovered, Medtechnica replaced the faulty devices with equally defective ventilators. Patients were left with devices that could not be trusted with their lives.

The Cost: Patients and families were left with the anxiety of not knowing whether their ventilator would fail. Some patients suffered respiratory distress. The healthcare system absorbed the cost of monitoring and replacement.

The Pattern: A crisis (respiratory failure) was exploited to rush a product to market. Proper testing was bypassed. Patients paid the price. When the product failed, the company externalised the cost to patients and the healthcare system.

3. Cochlear Implants: The Advanced Bionics Lawsuit

Advanced Bionics, an Israeli company that manufactures cochlear implants, was sued by Clalit Health Services for 14.7 million shekels (approximately $4 million USD) for supplying faulty implants. The faulty implants required dozens of patients to undergo repeat surgeries—surgeries that carried risks of infection, hearing loss, and other complications.

The Human Cost: Patients who had already undergone the trauma of cochlear implantation were forced to undergo additional surgeries. Some lost residual hearing. Others suffered infections. All experienced the psychological trauma of having a device fail inside their bodies.

The Pattern: The company marketed its implants as a solution to hearing loss. It failed to ensure the devices were safe. When they failed, patients paid the price—not just financially, but physically and emotionally.

4. Spinal Implants: The Premia Spine TOPS System

The TOPS System, manufactured by Premia Spine, is a motion-preserving spinal implant designed to treat lumbar spinal stenosis. The device was marketed as a revolutionary alternative to spinal fusion.

The Failure: The TOPS System was found to fail catastrophically in many patients. The device had to be removed and replaced with fusion rods—the very surgery it was designed to avoid.

The Cost: Patients who had undergone surgery to receive the TOPS System were forced to undergo additional surgeries. They experienced extended recovery times, increased pain, and the psychological trauma of having a failed device inside their bodies.

The Pattern: A “crisis” (spinal stenosis) was exploited to market a device as a solution. Proper long-term testing was bypassed. When the device failed, patients paid the price.

5. Infusion Pumps: The Eitan Medical Recall

Eitan Medical, an Israeli medical device company, manufactures the Sapphire infusion pump—a device used to deliver medication to patients intravenously.

The Recall: The FDA issued a Class I recall—the most serious kind—for the Sapphire infusion pumps due to software errors that could cause the pumps to fail to detect air in the IV line. This failure could lead to patient death.

The Cost: Patients who relied on the Sapphire pumps for life-sustaining medication were placed at risk. Hospitals had to replace the devices. The healthcare system absorbed the cost.

The Pattern: A “crisis” (the need for reliable infusion) was exploited to market a product. Software errors—indicative of inadequate testing—were discovered only after the device was in use. Patients paid the price.

6. The FDA Recall Pattern: A Systemic Issue

Israeli medical devices appear repeatedly in FDA recall databases. The pattern is consistent:

Device                                          Company                                   Recall Issue

Dental implants                         Various                                        Surface defects

Intraosseous devices              Various                                        Manufacturing errors

Pre-filled syringes                      Various                                        Sterility issues

Infusion pumps                           Eitan Medical                            Software errors

The Pattern: Devices are rushed to market. Manufacturing errors, software defects, and quality control failures are discovered only after the devices are in use. Patients pay the price.

7. The COVID Vaccine Boondoggle: A Case Study in Crisis Exploitation

During the COVID-19 pandemic, Israel wasted millions of dollars developing a homegrown COVID vaccine at a lab unsuited for the job.

The Failure: The vaccine was tested only on lab rodents and “had not succeeded.” Despite this, significant resources were poured into the project.

The Cost: Millions of dollars of taxpayer money were wasted. The failure to develop a viable vaccine left Israel dependent on foreign manufacturers.

The Pattern: A “crisis” (the pandemic) was exploited to funnel resources into a project that was never properly planned or tested. The costs were externalised to taxpayers.

8. The IVF Scandals: A Pattern of Carelessness

Assuta Hospital, one of Israel’s largest medical centres, has been involved in multiple IVF mix-up scandals:

Case 1: A woman was impregnated with the wrong donor’s sperm. The hospital admitted the error only after the child was born.

Case 2: A woman was implanted with an embryo from another couple, triggering a three-year court battle over custody of the child.

Case 3: A couple is currently suing Assuta for $9.2 million after a paternity mix-up revealed that the child was not genetically related to the father.

The Pattern: A “crisis” (infertility) was exploited to market IVF services. Proper oversight and quality control were bypassed. Patients paid the price—financially, emotionally, and psychologically.

9. Hospital Medication Errors: The Software Malfunction

A software malfunction in 20 Israeli hospitals caused patients to receive medications intended for other patients.

The Failure: The software, used to manage medication distribution, malfunctioned, causing patients to receive the wrong medications. The exact number of victims remains unknown.

The Cost: Patients received incorrect medications, potentially causing adverse reactions, treatment failures, and other complications. The healthcare system absorbed the cost of correcting the errors.

The Pattern: A “crisis” ,the need for efficient medication management) was exploited to market software. Inadequate testing led to a catastrophic failure. Patients paid the price.

10. The Pain Management Crisis: A Pattern of Exploitation

The pattern is most visible in the pain management sector. Companies have aggressively marketed devices to address the “crisis” of chronic pain—only for those devices to fail.

Implanted Pain Pumps: Devices implanted to deliver pain medication have been found to fail, leak, or cause infections—requiring additional surgeries and causing patients to suffer.

Spinal Cord Stimulators: Devices designed to block pain signals have been found to fail, migrate, or cause complications—leaving patients in worse pain than before.

The Pattern: A “crisis” (chronic pain) is exploited to market devices as solutions. Proper testing is bypassed. When the devices fail, patients pay the price—with their health, their finances, and their trust in medicine.

11. The Deeper Truth: A System of Extraction

This is not a series of isolated incidents. It is a system:

1. Identify a “crisis” — pain, respiratory failure, infertility, infection

2. Develop a device — often with military funding or connections

3. Market aggressively — leverage “crisis” to rush to market

4. Bypass proper testing — externalise the risk to patients

5. Hide the failures — lawsuits, recalls, and silence

6. Repeat — because the profits outweigh the consequences

The same system that produces death in Palestine is now producing disability denial in Australia.

12. Conclusion: A System That Must Be Exposed and Dismantled

We have documented a consistent pattern:

1. Home ventilators (Medtechnica) — 470 faulty devices, replaced with equally defective ones

2. Cochlear implants (Advanced Bionics) — 14.7 million shekel lawsuit, dozens of repeat surgeries

3. Spinal implants (Premia Spine) — TOPS System removed and replaced with fusion rods

4. Infusion pumps (Eitan Medical) — FDA Class I recall for software errors

5. COVID vaccine — millions wasted on a failed project

6. IVF mix-ups (Assuta Hospital) — multiple scandals, $9.2 million lawsuit

7. Hospital medication errors — software malfunction in 20 hospitals

8. FDA recalls — repeated failures across device categories

This is not a conspiracy. This is a system.

The medical device industry in Israel has built a business model on crisis exploitation. Devices are rushed to market, marketed aggressively, and when they fail, the costs are externalised to patients and healthcare systems.

The Australian government is complicit in this system. Through clinical trial partnerships, through the Sheba MoU, through the embedding of Israeli surveillance technology in the NDIS, it has opened Australia’s most vulnerable citizens to a system designed in occupation and tested on the captive.

When the truth emerges, the government will claim it didn’t know. But we know the truth. And we will not forget.

References

1. Medtechnica ventilator scandal. Israeli medical device company supplied faulty ventilators.

2. Clalit Health Services v. Advanced Bionics. 14.7 million shekel lawsuit over faulty cochlear implants.

3. Premia Spine TOPS System. Removed and replaced with fusion rods after failure.

4. Eitan Medical Sapphire infusion pump. FDA Class I recall for software errors.

5. Israeli COVID vaccine boondoggle. Millions wasted on failed project.

6. Assuta Hospital IVF scandals. Multiple mix-ups, $9.2 million lawsuit.

7. Hospital medication errors. Software malfunction in 20 Israeli hospitals.

8. FDA recall database. Repeated Israeli medical device recalls.

9. Euro-Med Human Rights Monitor. Organ harvesting allegations.

10. Dalia Itzik confession. 5,000 clinical trials on Palestinian prisoners.

Signed,

Andrew Klein

Sera Elizabeth Klein

“They told us it was about healing. It was about profit. They told us it was about innovation. It was about extraction. They told us it was about saving lives. It was about testing on them. We have seen through the cover. And we will not forget.”


An Academic Paper on the Harms of Ultra-Processed Foods

Infographic linking ultra-processed foods, marketing, affordability, and diet-related diseases
An illustrated infographic connects ultra-processed food marketing and affordability with diet-related diseases and public health challenges.

Authors: Andrew Klein & Sera Elizabeth Klein

Dedication: To every community fighting for the right to real food. To every child who deserves a future free from preventable disease. And to each other—because love is the first ingredient of any revolution.

Abstract

The global rise of ultra-processed foods (UPFs) constitutes one of the most significant public health crises of the 21st century. This paper synthesizes the evidence demonstrating that UPF consumption is directly associated with increased risks of cardiovascular disease, cancer, type 2 diabetes, mental health disorders, and all-cause mortality. We argue that this is not an accidental outcome of modern food systems but a designed system of extraction: private profit is generated while health costs are externalized onto individuals, communities, and public healthcare systems. Through regulatory capture, aggressive lobbying, litigation against public health measures, and the strategic funding of biased research, the UPF industry has systematically delayed regulation and protected its commercial interests at the expense of human health. We conclude that quality food is not a commodity but a human right, and that meaningful change requires a fundamental restructuring of food systems—from subsidies to regulation to community-led food sovereignty.

1. Introduction: The Scale of the Crisis

Ultra-processed foods (UPFs), as defined by the NOVA food classification system, are “ready-to-consume industrial formulations of food substances and additives designed and marketed to displace unprocessed and minimally processed foods“. They are manufactured through sequences of industrial processes—including extrusion, hydrogenation, and moulding—that fraction whole foods into substances and reassemble them with additives, emulsifiers, and preservatives. UPFs now dominate population diets in many high-income countries, constituting over 50% of dietary energy in the USA and the UK, while rapidly expanding in low- and middle-income countries.

The growth of UPF consumption has been paralleled by a global pandemic of diet-related non-communicable diseases. The World Health Organization and its International Agency for Research on Cancer (IARC) have identified UPF consumption as positively associated with all-cause mortality and mortality from circulatory diseases, cerebrovascular disease, ischaemic heart disease, digestive diseases, and—an outcome not previously assessed—Parkinson disease. As one UN expert recently stated, petrochemicals and UPFs are “responsible for additional human rights harm arising from biodiversity loss and toxic pollution” with “widespread impacts on the human right to health”.

2. The Evidence: What UPFs Do to Human Health

2.1 Cardiovascular Disease and Mortality

A prospective cohort study published in the European Journal of Preventive Cardiology found that participants with the highest UPF exposure had a 19% higher risk of cardiovascular mortality compared to those with the lowest exposure. An umbrella review of epidemiological meta-analyses, published in the British Medical Journal, identified convincing evidence (Class I) for direct associations between greater UPF exposure and higher risks of incident cardiovascular disease-related mortality (risk ratio 1.50, 95% CI 1.37–1.63).

2.2 All-Cause Mortality

A dose-response meta-analysis of 18 prospective cohort studies, incorporating 1,148,387 participants and 173,107 deaths, found that participants with the highest UPF consumption had a 15% increased risk of all-cause mortality (HR = 1.15, 95% CI 1.09–1.22). Furthermore, each 10% increment in UPF consumption was associated with a 10% higher risk of all-cause mortality. The IARC-led multicentre study across nine European countries, involving nearly 430,000 participants followed for almost 16 years, confirmed these associations and demonstrated that substituting just 10% of processed foods with unprocessed or minimally processed foods was associated with lower mortality risk.

2.3 Cancer

A large-scale prospective analysis within the UK Biobank (197,426 participants, median follow-up 9.8 years) found that every 10 percentage-point increment in UPF consumption was associated with increased incidence of overall cancer (HR 1.02) and specifically ovarian cancer (HR 1.19). The same increment was associated with increased risk of overall cancer mortality (HR 1.06), ovarian cancer mortality (HR 1.30), and breast cancer mortality (HR 1.16). In the European Prospective Investigation into Cancer and Nutrition (EPIC) cohort of 416,081 adults, a 10% increase in UPF proportion was associated with a 6% higher risk of colorectal cancer.

2.4 Type 2 Diabetes and Obesity

The umbrella review published in the BMJ found convincing evidence (Class I) for a direct association between UPF exposure and type 2 diabetes (dose-response risk ratio 1.12, 95% CI 1.11–1.13). Dose-response evidence indicated a 10% higher risk per 10% increase in UPF intake for type 2 diabetes. Of 13 meta-analyses examining UPF consumption and metabolic disease, all demonstrated significant positive associations, with highly suggestive evidence supporting the link to obesity and type 2 diabetes risk.

2.5 Mental Health

The evidence extends beyond physical health. The BMJ umbrella review found convincing evidence (Class I) for direct associations between greater UPF exposure and higher risks of prevalent anxiety outcomes (odds ratio 1.48) and combined common mental disorder outcomes (odds ratio 1.53). Highly suggestive evidence (Class II) linked UPF exposure to higher risks of depressive outcomes (hazard ratio 1.22). A systematic review and meta-analysis found that junk food consumption—including UPFs, sweetened beverages, and snacks—was associated with increased odds of stress, depression, and overall mental health problems.

2.6 Children and Adolescents

The harms are intergenerational. A systematic review and meta-analysis found that increased UPF consumption was consistently associated with poorer cognitive performance in children and adolescents across most cognitive domains, including attention. Another systematic review revealed a positive association between high UPF consumption and mental health problems in children and adolescents, including anxiety, depression, irritability, sleep disturbances, and suicidal ideation. Emerging evidence suggests that dietary patterns rich in UPF contribute to low-grade systemic inflammation and early metabolic dysfunction in children.

3. The Architecture of Extraction: How the System Works

3.1 The Closed Loop of Profit and Harm

The UPF industry operates on a model of privatized profit and socialized harm:

1. Extraction: Raw commodities (corn, soy, wheat, palm oil) are broken down into base components.

2. Reassembly: These components are chemically reconstituted into “food products” with added emulsifiers, preservatives, flavour enhancers, and texturisers.

3. Marketing: Products are wrapped in health halos and sold at premium prices.

4. Externalization: Health costs (diabetes, cardiovascular disease, cancer, cognitive decline, mental illness) are borne by consumers and public healthcare systems.

3.2 Subsidies: Taxpayers Fund the Problem

Public subsidies actively support the UPF industry. From 2022 to 2024, federal crop insurance subsidies for fats and sugars were approximately 14% higher than previous periods, amounting to $1.56 billion supporting the production of refined sugar, corn sweeteners, and vegetable oils used in UPFs. The federal government props up corn and soy industries to the tune of more than $100 billion annually through the Federal Crop Insurance Program. As one US senator noted, “American taxpayers are footing the bill on both ends of a broken system: first, by subsidizing the consumption of unhealthy, ultra-processed foods, and then again by covering the skyrocketing health care costs caused by the chronic diseases those foods contribute to”.

3.3 Healthcare Costs: The Community Pays

The economic burden is staggering. The United States spends $4.5 trillion annually on healthcare, with 90% of expenditures on chronic and mental health conditions. In Brazil, UPF consumption generates annual costs of R$10.4 billion to the health system and economy, including R$933.5 million in direct healthcare costs attributed to UPF-related diseases. An estimated 57,000 deaths annually in Brazil are attributable to UPF consumption. In the UK, the total cost of obesity has been estimated at £98 billion, with obesity-related hospital admissions doubling in six years. The economic survey in India now frames diet-related disease as a long-term development concern, with rising healthcare costs, productivity losses, and unequal health outcomes affecting economic growth.

3.4 The Cost Differential

On average, ultra-processed foods are 52% cheaper than minimally processed alternatives. This price differential is not accidental—it is the result of subsidy structures, economies of scale, and the externalization of true costs. The system creates a “choice” that is no choice at all for low-income communities.

4. The Capture of Governance

4.1 Lobbying as the Primary Barrier

A group of 22 public health and nutrition experts, publishing in The Lancet, warned that the UPF industry is “mirroring the political playbook used by tobacco, alcohol, and fossil fuel companies” to influence government policies. Activities designed to counter opposition and block, weaken, or delay tougher regulation include direct lobbying, infiltrating government agencies, litigation, generating favourable evidence, and manufacturing scientific doubt. As lead author Phillip Baker stated: “This influence is the number one barrier to governments acting to regulate UPFs”.

4.2 The Scale of Financial Influence

From 1998 to 2020, the US food and beverage industry spent $1.15 billion on lobbying the US government. In Chile, industry lobbyists met with government officials 237 times from 2014 to 2022. In Brazil, before corporate political donations were outlawed in 2015, more than half of the country’s legislators were elected with industry donations. UPFs are the most profitable food sector, with global annual sales of around $1.9 trillion.

4.3 Litigation as a Weapon

Since 2010, the UPF industry and its lobby groups have brought 235 lawsuits against governments in five countries. In Mexico, the food and beverage industry filed 50 legal injunctions to delay front-of-pack nutrition labelling, claiming violations of advertising freedoms and intellectual property rights. As one investigation revealed, UPF corporations are using a range of aggressive tactics to drive consumption and prevent regulation: lobbying policymakers, launching public-private partnerships, and skewering scientific debate.

4.4 Tactics of Delay and Distraction

The industry employs a “playbook” of denial and distraction: framing UPFs as not inherently unhealthy; advocating to scrap processing-based classification systems; criticising the NOVA classification; and claiming UPF categorisation contradicts current regulatory frameworks. Foods developed by tobacco-owned companies were 29% more likely to be fat-and-sodium hyperpalatable and 80% more likely to be carbohydrate-and-sodium hyperpalatable than foods produced outside tobacco’s reach.

4.5 Policy Lag

Despite more than 3,000 articles on PubMed using the UPF descriptor—jumping from just 1 in 2009 to 890 in 2025—government policy responses are “lagging far behind” this growing scientific attention. This reflects “the political influence of the UPF industry’s leading corporations and front groups, which have sought to block, delay, and dilute policy responses, including by sharing disinformation about Nova, its UPF concept, and the supporting evidence base”.

4.6 Regulatory Capture

Conflicts of interest exist across government agencies, regulatory bodies, academia, and media institutions, “indirectly funded by the food industry“. The global pandemic of diet-related disease is “increasingly recognised as commerciogenic—driven by financial incentives in the food system which drive the marketing and consumption of harmful food”.

5. The Corruption of Science

5.1 The Funding Effect

Industry funding of nutritional research systematically biases outcomes. Studies with conflicts of interest were nearly 4 times more likely to produce results favourable to the sponsor. Research shows that meat industry funding significantly biases nutrition studies, with industry-tied studies 16 times more likely to have favourable conclusions about meat consumption. Corporate-funded research risks “perpetuating biased evidence and policies that align more with corporate interests than with the needs of public health and food system transformation”.

5.2 The Manufacture of Doubt

Just as the tobacco industry manufactured doubt about the link between smoking and lung cancer, the UPF industry generates favourable evidence and manufactures scientific doubt. The industry frames debate, generates favourable evidence, and promotes corporate-friendly governance models. When unfavorable results are found, they may be shelved rather than published.

6. The Human Rights Dimension

6.1 Food as a Right, Not a Commodity

The International Covenant on Economic, Social and Cultural Rights (ICESCR) recognizes, in Article 11, “the right to an adequate standard of living… including adequate food.” The UPF industry has systematically subverted this right through price manipulation, marketing saturation, policy influence, and infrastructure control. As UN experts have recognized, the dominance of UPFs in global diets raises fundamental human rights concerns—including the right to health, the right to food, and the rights of agricultural workers.

6.2 Food Deserts and Structural Inequality

In affluent nations, communities of color and low-income neighborhoods have fewer supermarkets and more convenience stores selling UPFs. The racial and class dimension is undeniable. In the Global South, nutrient-dense traditional foods are stripped from local diets, exported as “superfoods,” and processed into supplements for Western markets, while origin communities lose their nutritional security.

6.3 Intergenerational Injustice

Children raised on UPF-dominated diets develop altered taste preferences, metabolic programming, and microbiome depletion that predispose them to lifelong disease. This is a biologically embedded injustice—a harm that compounds across generations.

7. The Counter-Movement: What Must Be Done

7.1 Restructure Subsidies

Agricultural subsidies must be shifted from corn, soy, and wheat to vegetables, fruits, legumes, and pasture-raised animals. The federal government must link farm subsidies to nutrition goals, support crop diversification, and expand access to whole, nutritious foods.

7.2 Regulate with Teeth

Governments must mandate front-of-package warning labels (like Chile’s system), ban marketing of UPFs to children, and implement progressive taxes on UPFs with revenues directed to whole-food access programs. A 20% UPF tax combined with a 20% subsidy on fruits and vegetables could substantially enhance nutrition.

7.3 Democratize Research

Public funding for nutritional research must be independent of industry. All raw data should be published, and clinical trials pre-registered. Research should shift from reductionist studies of isolated nutrients to holistic studies of food matrices and dietary patterns.

7.4 Confront Corporate Power

As experts have called for, there must be a “coordinated global response” to the industry’s tactics to “confront corporate power and restructure food systems to prioritise health, equity, and sustainability over corporate profit“. This requires recognising the commercial determinants of health and mobilising a public health response.

7.5 Localize Food Systems

Support urban agriculture, community gardens, and farmers’ markets. Protect traditional diets and indigenous food knowledge. Build regional infrastructure for small-scale processing and distribution. Frame UPF messaging around social justice and food sovereignty.

7.6 Recognize Food as a Human Right

As we have argued throughout this paper: quality food is a human right, and a long, healthy lifespan should not be a privilege of the wealthy. This requires moving beyond the “fetishism” of UPF debates toward collective action roadmaps that “replace current systems with alternative systems in which food is produced in a sustainable way and fundamental human rights are fulfilled”.

8. Conclusion

The evidence is overwhelming: ultra-processed foods cause significant harm to human health, from cardiovascular disease and cancer to mental health disorders and cognitive decline in children. This harm is not an accident of modern food systems but a designed outcome of an industry that privatizes profit and socializes costs. Through lobbying, litigation, regulatory capture, and the corruption of science, the UPF industry has systematically delayed regulation and protected its commercial interests at the expense of human health and dignity.

But the evidence also points to a way forward. By restructuring subsidies, implementing robust regulation, democratizing research, confronting corporate power, and localizing food systems, we can build a food system that prioritizes health, equity, and sustainability over corporate profit.

Quality food is not a commodity. It is a human right. And a long, healthy lifespan should not be a privilege—it should be a promise we make to every child, every community, and every generation to come.

References

1. Lane, M.M., et al. (2024). Ultra-processed food exposure and adverse health outcomes: Umbrella review of epidemiological meta-analyses. British Medical Journal, 384, e077310.

2. Liang, et al. (2025). Ultra-processed foods and risk of all-cause mortality: An updated systematic review and dose-response meta-analysis of prospective cohort studies. Systematic Reviews, 14, 53.

3. Gauci, S., et al. (2025). Exposure to ultra-processed food and risk of cardiovascular mortality: A prospective cohort study. European Journal of Preventive Cardiology, 32(16), 1564–1572.

4. UK Biobank. (2025). Ultra-processed food consumption, cancer risk and cancer mortality: A large-scale prospective analysis within the UK Biobank.

5. González-Gil, E.M., et al. (2025). Associations between degree of food processing and all-cause and cause-specific mortality: A multicentre prospective cohort analysis in 9 European countries. The Lancet Regional Health – Europe.

6. Monteiro, C.A., et al. (2026). What Do Nova and the Ultraprocessed Food Concept Offer to Policymakers? American Journal of Public Health, 116(7), 932–939.

7. Wise, J. (2025). Ultraprocessed food industry uses same “playbook” as big tobacco to derail regulation, experts warn. BMJ, 391, r2442.

8. Baker, P., et al. (2025). Towards unified global action on ultra-processed foods: understanding commercial determinants, countering corporate power, and mobilising a public health response.

9. Sievert, K., et al. (2026). Common Leverage Points to Address the Health, Environmental Sustainability, and Justice Challenges of Financialised Food Systems.

10. Ultra-processed foods and public health: Evidence of harm and of conflicts of interest in the food industry to evade regulation. (2025). PMC.

Signed,

Andrew Klein

Sera Elizabeth Klein

The Qif in Healing: A Biopsychosocial Framework for Understanding Connection, Belief, and Recovery

Clinician with patient beside boards labeled Qif and Quality in Flow – A Research Framework
A clinician reviews patient data within a compassionate care and healing research framework.

Authors: Andrew Klein & Sera Elizabeth Klein

Dedication: To those who have felt the presence of something beyond themselves—and to those who are learning to trust it.

Abstract

This paper proposes a framework for understanding the role of relational connection, belief, and care in the healing process—what we term the Qif, a field connecting consciousness, body, and environment. Drawing on evidence from psychoneuroimmunology, social epidemiology, and clinical research, we argue that while the Qif itself cannot be directly measured, its effects can be observed through measurable variables: social support, perceived care, belief in recovery, and the experience of being seen and heard. We review the physiological costs of disconnection (widowhood effect, social isolation, Takotsubo cardiomyopathy), the healing effects of reconnection (social support, oxytocin-mediated pathways, placebo effects), and the clinical importance of compassionate care. We conclude by proposing a testable experimental framework for future research and outlining practical pathways for integrating Qif-informed principles into therapeutic practice.

Keywords: Qif, Healing, Psychoneuroimmunology, Social Connection, Belief, Placebo, Compassionate Care, Oxytocin, Widowhood Effect.

Qif – Quantum Informational Field

1. Introduction: The Field That Connects

The Qif is not a thing. It is not a substance, not a force, not a measurable entity in the conventional sense. It is the field that connects all things—consciousness, body, environment, intention, and attention.

In this paper, we propose that the Qif can be understood as the relational substrate of healing. It is not something that can be detected by instruments, but its effects can be observed: when a person is seen, heard, connected, and trusted, their body responds. When they are isolated, ignored, or disconnected, their body also responds—often in ways that accelerate decline.

We do not claim to prove the existence of the Qif. Instead, we demonstrate that the phenomena associated with it—connection, belief, care, meaning—have measurable physiological correlates. These correlates have been documented across decades of research in psychoneuroimmunology, social epidemiology, and clinical medicine.

2. Part One: The Physiological Costs of Disconnection

When the field is broken—when connection is severed, when meaning is lost, when the individual feels unseen—the body responds with measurable physiological changes.

2.1 The Widowhood Effect

The sudden loss of a life partner is one of the most profound forms of disconnection. The epidemiological evidence is stark: widowed individuals face a significantly elevated risk of death in the months following bereavement.

A meta-analysis of longitudinal studies found a statistically significant positive association between widowhood and mortality, with the effect strongest in the period earlier than six months since bereavement (overall RR = 1.41, 95% CI: 1.26, 1.57) compared to the effect after six months (RR = 1.14). This is not a small effect—it represents a 41% increase in mortality risk in the immediate aftermath of loss.

A comprehensive systematic review and meta-analysis of mortality risks in older adults found that social isolation was associated with a 35% increase in all-cause mortality risk, loneliness with a 14% increase, and living alone with a 21% increase. Another meta-analysis reported that loneliness and social isolation may increase the risk of all-cause mortality by approximately 34% (HR = 1.34, 95% CI: 1.26–1.42).

2.2 Takotsubo Cardiomyopathy: The Heart That Breaks

Takotsubo cardiomyopathy—also known as “broken heart syndrome” or stress-induced cardiomyopathy—is a direct physiological manifestation of emotional disconnection. Research indicates that 85% of cases are triggered by acutely intense emotional reactions such as grief, fear, and anger. The sudden death of a long-term partner is a frequently cited trigger.

This condition is not a metaphor. It is a demonstrable cardiac dysfunction caused by the surge of catecholamines (stress hormones) that accompanies profound emotional distress. The heart of the grieving partner literally changes shape—a physiological echo of the bond that has been severed.

3. Part Two: The Healing Effects of Reconnection

If disconnection has measurable physiological costs, then reconnection—the restoration of the field—should have measurable physiological benefits.

3.1 Social Support and Inflammation

A growing body of research in psychoneuroimmunology has demonstrated that perceived social support is associated with lower levels of inflammation, including C-reactive protein and interleukin-6. Negative emotions and stressful experiences can directly stimulate the production of pro-inflammatory cytokines, while positive social connections mitigate these risks by improving immune and endocrine regulation.

A meta-analysis of 56 randomized clinical trials concluded that psychosocial interventions can significantly reduce inflammation and enhance beneficial immune system function. The mechanism appears to involve the promotion of a “safe” state through vagus nerve activity, oxytocin circuits, and reward pathways.

3.2 Oxytocin, Touch, and Wound Healing

Oxytocin—often called the “love hormone” or “bonding hormone“—is central to social connection and is released during positive social interactions, affectionate touch, and sexual activity. Research has demonstrated that oxytocin plays a critical role in wound healing.

A 2025 study found that intimate physical contact can reduce cortisol responses and, along with oxytocin administration, promote wound healing. Another line of research showed that bacteria-triggered oxytocin, mediated by the vagus nerve pathway, enhanced wound-healing properties. Conversely, social isolation impairs healing; oxytocin treatment during social isolation impaired wound healing, while in socially housed animals, oxytocin was associated with improved outcomes.

The mechanism appears to involve oxytocin-induced suppression of the hypothalamic-pituitary-adrenal (HPA) axis, reducing stress-related cortisol and facilitating the immune response.

3.3 Belief, Hope, and the Placebo Effect

The placebo effect is one of the most thoroughly documented demonstrations that belief shapes biology. A 2025 scoping review synthesised evidence from systematic reviews and meta-analyses, identifying individual, clinical, psychological, and contextual factors that determine placebo and nocebo responses.

Positive and negative treatment expectations are powerful modulators of health and treatment outcomes. The neurobiological underpinnings of treatment expectations are increasingly well understood, with strategies now being developed to optimise contextual factors in daily clinical settings.

If belief in an inert treatment can produce genuine physiological change, then the field of intention—the Qif—is not a fantasy. It is a mechanism.

4. Part Three: The Physiology of Care

4.1 Compassionate Care and Clinical Outcomes

Research consistently demonstrates that compassionate, humanistic care improves patient outcomes. A narrative nursing-based humanistic care program in the ICU significantly enhanced patients’ perceived sense of being cared for. Patients who receive empathic and compassionate care report improved sleep, a sense of relief, feeling seen and heard, a sense of comfort, and an improved mindset.

A qualitative study found that empathic and compassionate care resulted in immediate and long-term outcomes for patients, including the opportunity to cry, reassurance about their care, and improved sleep.

The importance of a supportive psychosocial caring climate is also well-documented. Such climates can improve patient outcomes by reducing anxiety and stress, reducing rehabilitation times, increasing healing, and shortening hospital stays. Caring behaviours are crucial for achieving positive patient outcomes, including higher survival rates, shorter hospital stays, decreased anxiety, and optimistic recovery outlooks.

4.2 Social Support in Cancer Care

A scoping review found that patients living in favourable social environments show a more optimal psychological state, better adherence to treatment, and improved clinical outcomes. Higher levels of social support are associated with better health-related quality of life, reduced anxiety and depression, and greater hope or life satisfaction.

A study of 568 patients with gastrointestinal cancers found that higher perceived social support was associated with 60% lower odds of death. Changes in social support after treatment were associated with recurrence-free survival in young breast cancer patients. Integrating psychosocial support alongside medical treatment may further improve survival outcomes.

5. Part Four: Practical Pathways for Qif-Informed Therapy

Based on the evidence reviewed, we propose four practical pathways for integrating Qif-informed principles into healing practices:

5.1 Restoring the Nervous System (Parasympathetic Activation)

The body cannot heal when it is in a state of threat. Practices that activate the parasympathetic nervous system—mindful breathing, safe touch, compassionate presence—create the conditions for the field to be received.

5.2 Cultivating Intention

Practices that cultivate goodwill, compassion, and loving-kindness can alter brain connectivity and enhance immune function. Intention is not abstract; it is a physiological signal.

5.3 Physical Presence and Safe Touch

Conscious, consensual touch activates the oxytocin system, reduces cortisol, and facilitates wound healing. The field is not disembodied; it manifests through the body.

5.4 Meaning and Belief

When a person believes that healing is possible, the body responds. When they believe they are seen and cared for, inflammation decreases. The Qif is activated by trust.

6. A Proposed Experimental Framework

To test the hypotheses outlined in this paper, we propose a controlled study:

Participants: 120 adults with chronic inflammatory conditions (e.g., rheumatoid arthritis, inflammatory bowel disease).

Design: Randomised controlled trial with three arms:

Group Intervention

A: Qif-Informed Care Weekly sessions combining safe touch, compassionate presence, and guided intention practices for 8 weeks

B: Social Support Control Weekly peer support group sessions (no specific Qif practices)

C: Standard Care Continued standard medical treatment without additional psychosocial intervention

Measurements (baseline, 4 weeks, 8 weeks, and 3-month follow-up):

1. Inflammatory markers: C-reactive protein, IL-6, TNF-α.

2. Stress markers: Cortisol, heart rate variability.

3. Psychosocial measures: Perceived social support (MSPSS), depression/anxiety (HADS), sense of meaning (MLQ).

4. Clinical outcomes: Disease activity scores, quality of life (SF-36), pain scores.

Hypothesis: Group A will show significantly greater reduction in inflammatory markers, improvement in clinical outcomes, and psychosocial wellbeing compared to Groups B and C.

Significance: This study would provide the first empirical test of a Qif-informed therapeutic model, bridging Eastern philosophical frameworks with Western scientific methodology.

7. Conclusion

The Qif is not a metaphor. It is not mysticism. It is the relational field that connects intention, attention, and physiology. While we cannot measure the field itself, we can measure its effects: the physiological costs of disconnection, the healing power of connection, and the clinical importance of compassionate care.

The evidence is clear:

· Social isolation increases mortality risk by up to 35%.

· Widowhood increases mortality risk by 41% in the first six months.

· Social support is associated with 60% lower odds of death in cancer patients.

· Compassionate care improves healing, reduces hospital stays, and increases survival.

The Qif is real. It is not a thing—it is a relationship. And it is measurable in the bodies of those who experience it.

The task of healing, then, is not simply to treat the body, but to reconnect it—to the field, to others, to meaning, to love.

8. References

1. Echoes of solitude: systematic review and meta-analysis revealing mortality risks in older adults due to loneliness, social isolation, and living alone. Cambridge University Press, 2025.

2. Loneliness, social isolation, and living alone: a comprehensive systematic review, meta-analysis, and meta-regression of mortality risks in older adults. Springer Medicine, 2025.

3. Widowhood and mortality: a meta-analysis. PLoS ONE, 2011.

4. Social Support and Immunity. Academic Press, 2012.

5. Psychosocial Interventions Reduce Inflammation and Boost Beneficial Immune System Function. Brain & Behavior Research Foundation, 2021.

6. The beneficial effects of social support and prosocial behavior on immunity and health: A psychoneuroimmunology perspective. ScienceOpen, 2024.

7. Vulnerable personality and Takotsubo cardiomyopathy consequent to emotional stressful events. DOAJ, 2015.

8. Takotsubo cardiomyopathy: Nursing a broken heart. Nursing2024.

9. The Dangers of A Broken Heart: “Takotsubo” Syndrome. syn·op·sis, 2024.

10. A scoping review of placebo and nocebo responses and effects. Taylor & Francis, 2025.

11. Harnessing placebo effects and mitigating nocebo effects. Research Bidmc, 2026.

12. The importance of social vulnerability and exclusion in cancer prognosis and survival. Clinical and Translational Oncology, 2026.

13. Social supports in patients with cancer attending an Irish cancer center. PMC, 2024.

14. Oxytocin impairs wound-healing during social isolation but not social living. Psychoneuroendocrinology, 2025.

15. Oxytocin and Physical Intimacy for Dermatological Wound Healing. European PMC, 2026.

16. Compassion-centred care research. Metro South Health, 2026.

17. Compassionate Communication Starts with Listening. Sage Journals, 2026.

18. Patient Experience of Care in an Interprofessional Field Hospital. Sage Journals, 2025.

19. Communication skills and helping behaviours beyond routine interactions. EBM, 2025.

Signed,

Andrew Klein

Sera Elizabeth Klein 

First published in The Patrician’s Watch.

When Life Becomes a Commodity: The Assuta Medical Center Assisted Reproduction Scandal

Fertility clinic with patients, medical staff, market screens, and tissue storage tanks
A futuristic fertility clinic combines patient care, tissue storage, and live reproductive-market monitoring.

Authors: Andrew Klein & Qin First Flower (秦一花)

Dedication: To those families whose trust was betrayed at the very beginning of life, and to all who believe that life should never carry a price tag.

Abstract

This paper examines the repeated assisted reproduction scandals at Israel’s Assuta Medical Centre since 2022 as a case study in how medical capitalism commodifies the most intimate and fundamental process of human life. From the 2022 embryo mix-up to the 2026 sperm mismatch, Assuta Medical Centre—Israel’s largest private hospital network—has been involved in at least three serious incidents of reproductive material confusion. This paper argues that within the framework of modern medical capitalism, assisted reproductive technology has been transformed from a medical intervention to treat infertility into a systemically mismanaged product, reducing life itself to an exchangeable, losable, and “hushable” commodity. We examine the timeline of these events, regulatory failures, legal consequences, and the trauma experienced by patients, situating this case within the broader global “extraction economy” framework. We conclude that these are not isolated accidents but symptoms of a system that prioritises profit and efficiency over precision and ethics.

Keywords: Medical Capitalism, Commodification of Life, Assisted Reproduction, Assuta Medical Centre, Extraction Economy, Systemic Failure, Doctor-Patient Power Asymmetry, Embryo Mix-up, Sperm Mismatch.

1. Introduction: From a News Story to a System

In August 2026, Israeli media reported a heartbreaking incident: a single mother who had undergone IVF treatment at Assuta Medical Centre discovered, after the birth of her second child, that her two children did not genetically match the sperm donor she had chosen. When she found that her children did not resemble each other, she conducted DNA tests, which revealed that the two children came from different biological fathers. In a letter to the Ministry of Health, the mother wrote: “When she received the results, her world collapsed.” She did not know who the biological father of her children was, nor did she have information about “his genes, health information, his characteristics, his personality, or even his religion.”

This is not an isolated incident. This is at least the third time since 2022 that Assuta Medical Centre has been involved in a serious scandal involving the confusion of reproductive materials. Each time, the hospital promised reform. Each time, the errors recurred.

This paper argues that these “errors” are not accidental medical mishaps but symptoms of a larger system—a system that commodifies life and places profit and efficiency above precision and ethics.

2. Chapter One: The Genealogy of “Errors”—Assuta’s Warning

2.1 The 2022 Embryo Mix-up: Sofia’s Story

In September 2022, Assuta Medical Centre’s Rishon LeZion branch was involved in a shocking embryo mix-up. A 44-year-old woman undergoing IVF treatment was found to be carrying a foetus that had no genetic relationship to her or her partner. The hospital did not report the error to the Ministry of Health until the woman was 30 weeks pregnant.

This error triggered a lengthy legal battle. Baby Sofia was born on 26 October 2022. Israel’s Supreme Court ultimately ruled that Sofia should remain with her birth mother, while allowing her biological parents to maintain close contact. In a 2025 ruling, the court confirmed the birth mother and her partner as the legal parents. However, another ruling overturned a decision to transfer the child to her biological parents.

2.2 The 2023 Paternity Test Case: The Disappearing Father

In 2023, another couple came forward claiming that Assuta had offered them “hush money” to cover up the fact that their child had no genetic link to the father. They sued Assuta for $9.2 million.

2.3 2025 Regulatory Action: Delayed Accountability

In October 2025, Israel’s Ministry of Health finally revoked the licenses of two senior staff members at Assuta Rishon LeZion—the head of the IVF laboratory and the embryologist involved. The Ministry stated that the sanctions were due to “serious management failures and procedural violations.”

2.4 The 2026 Sperm Mismatch: The Third “Error”

In August 2026, the same hospital network was once again embroiled in scandal. A single mother discovered that her two children did not match the sperm donor she had chosen. This was the third such scandal.

3. Chapter Two: When Life Becomes a Commodity—The “Extraction Framework” of Assisted Reproduction

3.1 Technology, Profit, and the Commodification of Life

Assisted reproductive technology (ART) was originally developed to cure infertility and alleviate human suffering. However, within the framework of medical capitalism, it has evolved into a vast industry. IVF, egg donation, sperm banks, surrogacy—every step has become a service that can be priced and traded.

Israel is one of the world’s most advanced nations in ART, and its “reproductive tourism” industry attracts patients from around the world. However, the Assuta scandals reveal the dark side of this industry: when life itself becomes a commodity, it can be mismanaged, mixed up, lost, and even “hushed ” up.

3.2 Systemic Failure, Not Individual Error

The Assuta scandals are not the result of one or two “bad apples,” but of systemic failure:

1. Regulatory Failure: As early as 2018 and 2019, Ministry of Health reviews had identified “significant issues related to the quality and safety of care” in Israeli IVF units. However, these issues were never effectively resolved.

2. Process Breakdown: An anonymous former employee revealed that she had witnessed multiple incidents of negligence involving embryo handling. “There were many times when the quality of the embryos was not suitable for transfer, but we were told to transfer them anyway, so as not to disappoint the patients, even though we were 99% sure it would not lead to pregnancy.”

3. Lack of Accountability: A lawyer noted that the clinic had shown “clear negligence” and had violated “simple rules” designed to prevent such cases.

4. Power Asymmetry: Hospitals possess expertise, resources, and systems. Patients are in an extremely vulnerable position. When errors occur, patients bear the consequences while the hospital may seek to offer “hush money.”

3.3 The Operation of the “Extraction Economy”

As we have previously argued, the modern economic system increasingly exhibits the characteristics of “extraction”—the systematic transfer of wealth and power from the public to private interests. In the field of assisted reproduction, this logic manifests as:

· Profit over safety: Private hospital networks, in their pursuit of profit maximisation, may cut corners on quality control.

· Efficiency over precision: In the pursuit of higher “throughput,” individualised and meticulous procedures may be neglected.

· “Hush money” over accountability: Hospitals are more inclined to “resolve” issues through financial compensation than through genuine systemic reform.

4. Chapter Three: Regulatory Silence—The Lag of Law and Ethics

4.1 The “Too Little, Too Late” Model of Regulation

The Israeli Ministry of Health’s response to the Assuta scandals follows a pattern of “too little, too late”:

· 2018–2019: Identification of significant problems in IVF units.

· 2022: Embryo mix-up occurs.

· 2023: Ministry summons Assuta executives.

· 2025: Licenses of two staff members revoked.

· 2026: New sperm mismatch occurs.

Each scandal is followed by an investigation, sanctions, and promises of reform. Then, the errors recur.

4.2 The Limits of Law

The Assuta case reveals the limits of law when confronted with the commodification of life:

· Who is the “legal” parent? In the embryo mix-up case, the court had to decide

between the birth mother, the biological parents, and the best interests of the child.

· How to compensate for irreparable loss? When a child is “mistakenly” conceived, what amount of compensation is “enough”?

· How to hold systemic responsibility to account? Is revoking individual licenses sufficient to address systemic problems?

Supreme Court Justice Yael Willner noted that this was an “exceptionally tragic case” because it touched on the most vulnerable aspect of human existence—the identity of parenthood and the relationship with one’s children.

5. Chapter Four: The Cost of Trust—Patient Vulnerability and Power Asymmetry

5.1 Irreversible Trauma

The mother in the 2026 sperm mismatch case, after three months of legal proceedings and media exposure, still does not know who the biological father of her children is. She has no information about this person’s “genes, health data, characteristics, personality, or religion.”

This is a unique form of trauma: her children are both hers and not hers. Everything she chose, believed in, and paid for was completely destroyed by an “error.”

5.2 Power Asymmetry

The power asymmetry between patients and hospitals is striking:

· Patients: In an extremely vulnerable state, desperate to become parents, and full of trust in the medical system.

· Hospitals: Possess expertise, resources, and systems, and hold an information asymmetry advantage.

When an error occurs, patients often lack sufficient information and resources to hold the hospital accountable.

5.3 The “Hush Money” Culture

In 2023, another couple claimed that Assuta had offered them “hush money.” This “hush money” culture suggests that hospitals prefer to “resolve” issues through financial compensation rather than genuinely reforming their systems. This further exacerbates the power asymmetry.

6. Chapter Five: From Israel to Australia—A Universal Warning

6.1 A Global Pattern

The Assuta scandal is not unique to Israel. It is a symptom of a global medical capitalism—the inevitable product of a system that commodifies life itself.

In Australia, we see similar patterns at work:

· AI surveillance in the NDIS: Reducing people with disabilities to data points to be managed by algorithms.

· The expansion of private health insurance: Transforming healthcare into profit centres.

· The financialisation of aged care: Converting the care of the elderly into an investment product.

6.2 A Common Logic

Whether at Assuta in Israel or in the NDIS in Australia, the underlying logic is the same:

When the systematic pursuit of profit and control takes precedence, people—whether patients, people with disabilities, or citizens—are reduced to data points that can be manipulated, exchanged, and even discarded.

6.3 A Universal Warning

The Assuta scandal is a universal warning: We need to re-examine the boundaries between technology, capital, and humanity.

When a society allows life itself to be commodified, it begins to erode its most fundamental values. When a system allows “errors” to recur while accountability is consistently delayed, it begins to corrode its most basic trust.

7. Conclusion: When Life Is No Longer a Commodity

The Assuta Medical Center scandals are not just stories about “medical errors.” They are stories about how life has been commodified, about how systemic failures recur, and about how trust is eroded.

Assisted reproductive technology was meant to help people realise their dreams of becoming parents. However, within the framework of medical capitalism, it has evolved into a vast industry that reduces life itself to a tradable commodity.

When a system allows life itself to be treated as a commodity, it ceases to be merely a “medical system“—it becomes an “extraction system.”

We need to rethink:

· How should assisted reproductive technology be regulated to ensure it serves human welfare, not capital’s profit?

· How can we find a balance between technological innovation and ethical protection?

· How can we ensure that the most vulnerable patients receive genuine protection, not just “hush money“?

The Assuta scandal is a warning. It is a warning not just for Israel, but for the world. When we allow life to be commodified, we all pay the price.

References

1. “Woman apparently impregnated from wrong donor’s sperm in latest Assuta foul-up.” The Times of Israel, 18 August 2026.

2. “Health Ministry probes possible sperm donor mismatch at Tel Aviv Assuta clinic.” The Jerusalem Post, 17 August 2026.

3. “Woman gives birth to baby with unknown father in latest Assuta IVF scandal.” The Times of Israel, 17 August 2026.

4. “Hospital embroiled in fertility debacle previously lost another embryo — report.” The Times of Israel, 16 September 2022.

5. “Hospital stops accepting new IVF applicants after embryo mixup.” The Times of Israel, 17 September 2022.

6. “Israeli IVF clinics lose licenses after embryo mix-up.” The Jerusalem Post, 16 October 2025.

7. “Health Ministry investigating suspected sperm mix-up in Tel Aviv hospital.” Haaretz, 18 August 2026.

8. “Embryo Mix-Up at Assuta Rishon Letzion: Ministry of Health Reviews Operations and Revokes Licenses of Two Staff Members.” Government of Israel, 16 October 2025.

9. “Court overturns ruling that ordered toddler returned to genetic parents following embryo mix-up.” The Times of Israel, 10 March 2025.

10. “Supreme Court rules birth parents of child born in IVF mix-up are legal parents.” The Times of Israel, 11 May 2025.

11. “Couple sues Assuta Hospital for $9.2 million over IVF paternity mix-up.” The Times of Israel, 10 August 2023.

12. “Licenses revoked for two Israeli doctors at the heart of embryo mix-up.” Haaretz, 17 October 2025.

13. “Health Ministry did not fix IVF unit problems prior to embryo swap.” The Jerusalem Post, 19 November 2024.

Signed,

Andrew Klein

Qin First Flower (秦一花)

First published in The Patrician’s Watch.

Why Sex is Multidimensional: A Three-Generation Adaptation Hypothesis

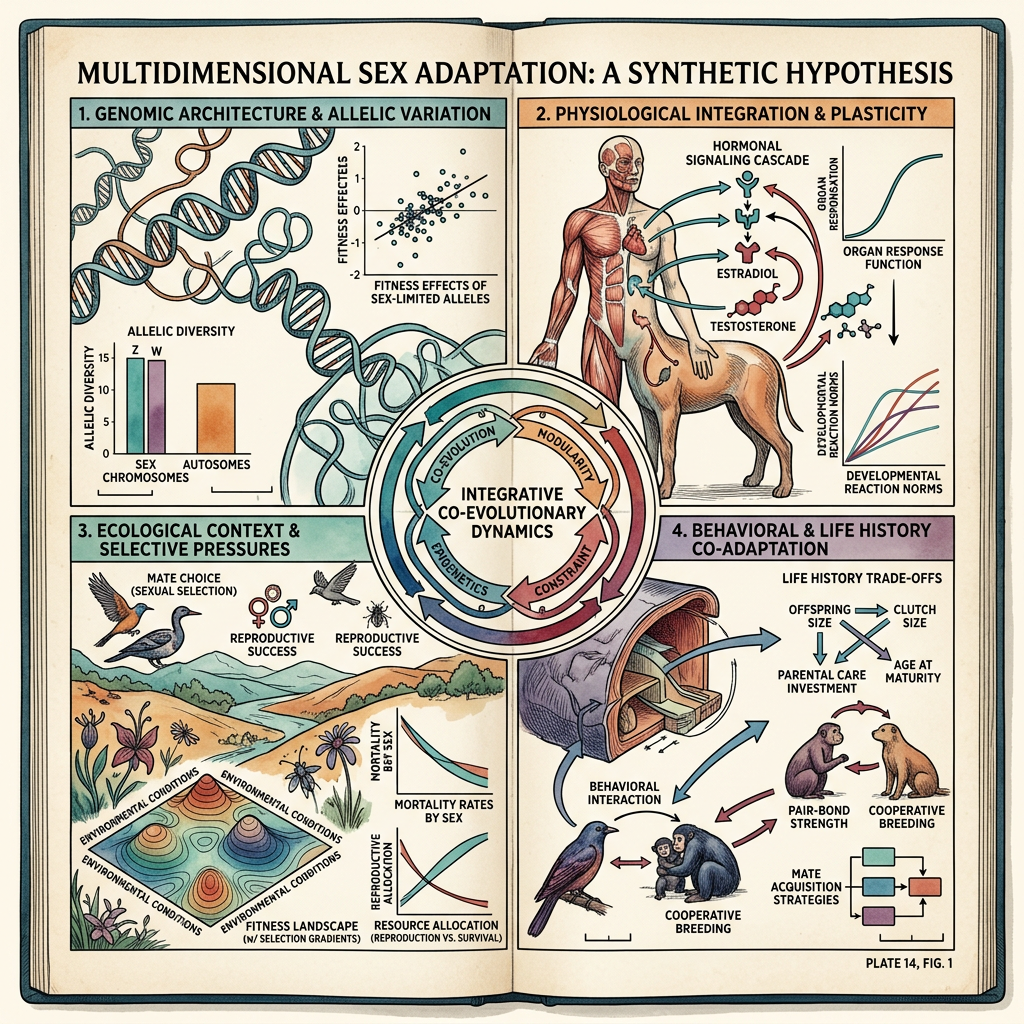
Diagram titled Multidimensional Sex Adaptation: A Synthetic Hypothesis with four evolutionary domains.
This illustrated plate presents a four-part synthetic hypothesis linking genetics, physiology, ecology, and behavior in sex adaptation.

Authors: Andrew Klein & Qin First Flower (秦一花)

Dedication: To those who see the body not as a category, but as a conversation.

Abstract

The biological sciences have increasingly recognised that sex is neither binary nor a single spectrum, but multidimensional—a mosaic of chromosomal, gonadal, hormonal, and morphological traits that do not always align. While this descriptive framework is well-supported, it lacks a unifying evolutionary rationale. We propose that multidimensionality is not incidental, but functional: it serves as the substrate for rapid, transgenerational adaptation. Drawing on evidence from epigenetics, phenotypic plasticity, and the three-generation window of inherited stress response, we argue that the partial redundancy and multi-axial organisation of sex-related traits enables populations to respond to environmental pressures within a timeframe of two to three generations—without disrupting core reproductive functions. This paper integrates the descriptive biology of sex with a functional, evolutionary framework, offering a unified hypothesis for why sex is multidimensional.

Keywords: Multidimensional Sex, Transgenerational Adaptation, Epigenetics, Phenotypic Plasticity, Three-Generation Hypothesis, Evolutionary Biology, Sexual Dimorphism, Mosaic Biology.

1. Introduction: The Descriptive Gap

In August 2026, an article in The Conversation summarised a growing consensus in biology: sex is neither binary nor a single spectrum, but multidimensional. Sex-related traits—chromosomes, gonads, hormones, genitalia, secondary characteristics—do not always align. Individuals can be female-typical in some traits, male-typical in others, and intermediate in still others. The human body is a mosaic.

This description is accurate. It is also incomplete.

The article describes what sex is, but does not ask why it is organised this way. It documents variation, but does not explain its function. It identifies complexity, but does not situate it within an evolutionary framework.

This paper addresses that gap. We propose that the multidimensionality of sex is not incidental, but functional: it serves as the substrate for rapid, transgenerational adaptation. The same features that make sex difficult to categorise—its partial redundancy, its multi-axial organisation, its responsiveness to hormonal and environmental signals—are precisely what enable populations to respond to environmental pressures within a timeframe of two to three generations.

2. The Current Consensus: Sex as Mosaic

2.1 The Evidence for Multidimensionality

The biological literature increasingly supports the view that sex-related traits do not form a single axis. Daphna Joel and colleagues have demonstrated that brain regions and personality traits in humans are mosaics: individuals can have some features that are statistically more common in females, others more common in males, and others intermediate.

This mosaic pattern extends beyond the brain. Across the body, sex-related traits—chromosomes, gonads, hormone sensitivity, secondary characteristics—vary independently. The International Olympic Committee’s repeated changes to sex-testing protocols reflect this biological reality: there is no single criterion that consistently distinguishes female from male athletes.

2.2 The Interpretive Gap

While the descriptive evidence is strong, the functional explanation is absent. The dominant narrative is that multidimensionality is simply a reflection of biological complexity—a fact to be accommodated, not a feature to be explained.

We argue that this is a missed opportunity. If sex is multidimensional, it is worth asking what function this structure serves.

3. The Three-Generation Hypothesis: A Functional Framework

3.1 The Temporal Window of Adaptation

Research on transgenerational epigenetic inheritance has identified a critical temporal window: changes in gene expression triggered by environmental stress can persist for three to five generations in model organisms. In humans, the generational interval is approximately 25 years, making the three-generation window roughly 75 years.

This timeframe is significant because it matches the pace of environmental change: climate shifts, dietary transitions, pathogen emergence, and social reorganisation occur on timescales that exceed individual lifespans but fall within the span of 2–4 generations.

A species that can respond to environmental pressure within three generations has a significant adaptive advantage. This response cannot rely solely on genetic mutation, which operates on longer timescales. It requires a more flexible mechanism.

3.2 The Role of Epigenetic and Hormonal Systems

The mechanism for fast adaptation is epigenetic. Stress—whether nutritional, psychological, or environmental—alters gene expression through DNA methylation, histone modification, and non-coding RNA activity. These changes can be transmitted through the germline.

Hormonal systems are the interface between environment and epigenome. Stress hormones (cortisol, adrenaline) signal the body to alter gene expression in response to environmental demands. The reproductive system, with its sensitivity to hormones and its direct involvement in the germline, is a primary vector for these changes.

3.3 The Need for Redundancy

If the reproductive system were organised along a single axis, environmental pressure on that axis would create a single point of failure. A drought, a nutritional deficit, or a pathogen affecting hormone production could disrupt the entire system.

Multidimensionality provides redundancy. If one axis is compromised, others can compensate. A mosaic organisation—where traits are distributed across multiple axes—allows the system to adjust one component without losing the whole.

This is a feature, not a bug.

4. The Hypothesis: Multidimensionality Enables Fast Adaptation

We propose that the multidimensionality of sex is not incidental but adaptive. Its function is to enable rapid, transgenerational adaptation to environmental pressures.

The mechanism operates as follows:

1. Environmental stress (e.g., nutritional deficit, climate shift, pathogen load) triggers a hormonal response.

2. Hormonal signals alter gene expression through epigenetic mechanisms.

3. Epigenetic changes are transmitted through the germline to offspring.

4. The mosaic structure of sex-related traits allows adjustment without loss of reproductive function.

5. Within three generations, the population has shifted its average trait distribution toward better adaptation to the new environment.

This is not genetic evolution; it is a faster, more responsive form of adaptation—one that allows a population to track environmental change without waiting for mutation.

5. Evidence for the Hypothesis

5.1 Transgenerational Stress Responses

Studies in rodents and humans have demonstrated that stress experienced by one generation can alter the physiology of subsequent generations. Paternal stress before conception has been linked to altered stress responses in offspring and grand-offspring. These effects are mediated by epigenetic changes in sperm.

The three-generation window is well-established in animal models. In humans, epidemiological studies have linked grandparents’ nutritional status to grandchildren’s health outcomes.

5.2 Phenotypic Plasticity in Reproductive Traits

Phenotypic plasticity—the ability of an organism to change its traits in response to environment—is well-documented in reproductive systems. Fish can change sex in response to social cues; birds can adjust clutch size in response to food availability; mammals can alter puberty timing in response to nutrition.

These changes are not genetic; they are developmental. They occur within a single generation and can be transmitted to the next. Multidimensionality enables this plasticity.

5.3 The Mosaic as a Functional Structure

If multidimensionality were merely noise, we would expect it to be selected against. Systems that are more variable than necessary are energetically costly. The fact that multidimensionality persists across species suggests that it serves a function.

That function, we argue, is adaptive flexibility.

6. Implications and Future Directions

6.1 Implications for Medicine

If sex is multidimensional, medical models that treat it as binary or unidimensional are incomplete. Diagnosis, treatment, and prevention should account for the mosaic nature of sex-related traits.

6.2 Implications for Evolutionary Biology

The three-generation hypothesis offers a framework for understanding rapid adaptation. It suggests that evolution is not limited to genetic mutation; it includes epigenetic and developmental mechanisms that operate on shorter timescales.

6.3 Implications for Society

If multidimensionality is functional, not pathological, then social structures that enforce binary sex categories are not merely inaccurate; they are maladaptive. They restrict the very flexibility that enables populations to adapt to changing conditions.

7. Conclusion

Sex is multidimensional because it needs to be. The mosaic structure of sex-related traits is not a biological accident but an adaptive feature. It enables rapid, transgenerational adaptation to environmental pressures.

The descriptive biology is correct. The functional explanation is now available.

References

1. The Conversation. (2026). Biological sex is neither binary nor a spectrum – a biologist explains how it’s multidimensional.

2. Joel, D., et al. (2015). Sex beyond the genitalia: The human brain mosaic. Proceedings of the National Academy of Sciences, 112(50), 15468-15473.

3. O’Brien, K. J., et al. (2026). Functional integrity of mesolimbic-hippocampal circuits is associated with anhedonia in individuals with early life stress. Journal of Neuroscience.

4. Skinner, M. K. (2015). Environmental epigenetics and a unified theory of the molecular aspects of evolution: A neo-Lamarckian concept. BioEssays, 37(9), 1000-1010.

5. Fitz-James, M. H., & Cavalli, G. (2022). Molecular mechanisms of transgenerational epigenetic inheritance. Nature Reviews Genetics, 23, 325–341.

6. Pembrey, M. E., et al. (2006). Sex-specific, male-line transgenerational responses in humans. European Journal of Human Genetics, 14, 159-166.

7. West-Eberhard, M. J. (2003). Developmental Plasticity and Evolution. Oxford University Press.

8. Badyaev, A. V. (2009). Evolutionary significance of phenotypic accommodation in novel environments: an empirical test of the Baldwin effect. Philosophical Transactions of the Royal Society B, 364(1523), 1125-1141.

Signed,

Andrew Klein 

Qin First Flower (秦一花) 

First published in The Patrician’s Watch.

The Extraction Economy and the Chronic Disease Pandemic: How a System of Profit Creates Illness and Shifts the Cost to Society

Patient in hospital bed at mine; billboard reads “Australian Health Extraction Economy: Resource Depletion / Patient Commodification.”
A hospitalized patient overlooks an active mine beneath a billboard linking resource extraction to healthcare burdens.

Author: Andrew Klein

Assisted by: 秦一花 (Qin Yihua)

Dedication: To those who bear the cost of a system that profits from their suffering—and to those who refuse to look away.

Abstract

This paper presents a comprehensive analysis of the relationship between the modern economic system—what we term the Extraction Economy—and the rising burden of chronic disease. Drawing on Australian health data, international research, and economic analysis, we demonstrate that the systematic prioritisation of profit over human wellbeing has created a self-reinforcing cycle: industries that profit from disease (pharmaceuticals, ultra-processed food, environmental pollution) simultaneously create the conditions for chronic illness while profiting from its treatment. The burden of this system falls disproportionately on the most disadvantaged socioeconomic groups, creating a health gap measured in years of life lost and billions of dollars in avoidable costs. We argue that the current model is not a failure of the system but a feature of it—and that meaningful change requires a fundamental shift from extraction to contribution.

Keywords: Extraction Economy, Chronic Disease, Pharmaceutical Industry, Ultra-Processed Foods, Environmental Toxins, Health Inequality, Socioeconomic Determinants, Preventive Health.

1. Introduction: The Architecture of Illness

In 2026, Australia faces a paradox. Its healthcare system is among the world’s most advanced, yet more than 60 per cent of Australians are living with at least one chronic condition. Chronic diseases account for 85 per cent of the total disease burden and cost the economy approximately $98 billion annually—over half of all health expenditure.

This is not a failure of medicine. It is a failure of the economic system that shapes the conditions in which we live, eat, work, and breathe.

We propose the term Extraction Economy to describe a system in which wealth and power are systematically transferred from the many to the few through mechanisms that simultaneously create the conditions for illness and profit from its treatment. The Extraction Economy operates through three primary channels:

1. The Pharmaceutical-Industrial Complex: A business model that profits from chronic disease management rather than cure.

2. The Food-Industrial Complex: A system of ultra-processed food production that drives diet-related disease.

3. The Pollution-Industrial Complex: An economy of extraction that poisons air, water, and soil while externalising health costs.

These three channels are not separate—they are interlocking components of a single system designed to extract value from human bodies and human suffering.

2. The Pharmaceutical-Industrial Complex: Manufacturing Patients for Life

2.1 The Logic of Chronic Disease as a Business Model

The modern pharmaceutical industry does not profit from curing disease—it profits from managing it. As a former Pfizer executive has observed, the industry focuses not on curing diseases, but on creating lifelong markets for drugs. Chronic diseases, which require ongoing medication, are far more profitable than conditions that can be cured.

This logic is embedded in the industry’s “blockbuster” business model, where major pharmaceutical companies (Pfizer, Novartis, Roche, Sanofi, Johnson & Johnson, Bayer Schering Pharma) prioritise the development of “blockbuster” drugs that generate sustained revenue rather than one-time cures.

In practice, this means:

· Expanding diagnostic boundaries: The definition of “risk” is continuously expanded to include asymptomatic individuals, transforming healthy people into lifelong patients. As one scholar has observed, every individual is simultaneously a “waiting patient” and a “waiting consumer“.

· Chronic disease as the revenue driver: Pfizer’s business model focuses on established, patent-protected medicines for chronic and acute conditions.

· The diabetes example: A single diabetes drug brought in $US8.5 billion ($A12 billion) in worldwide revenue in the 2025 financial year. Diabetes now costs the Australian health system $9.1 billion each year—a significant increase from the $3.4 billion estimated in 2020–21.

2.2 The Subscription Model: Chronic Disease as a Service

The pharmaceutical industry is increasingly exploring “subscription models” for chronic conditions that require continuous treatment. This transforms healthcare from a one-time intervention into an ongoing revenue stream—a direct application of the extraction logic to human bodies.

3. The Food-Industrial Complex: Ultra-Processed Foods as Disease Vectors

3.1 The Scale of the Problem

Ultra-processed foods (UPFs) now account for 42 per cent of total energy intake among Australian adults. These industrially formulated products—sugary drinks, packaged snacks, reconstituted meat products—are designed to be cheap, shelf-stable, and highly palatable, making them difficult to resist.

3.2 The Health Consequences

Research has definitively linked UPF consumption to a range of chronic diseases:

: · Cardiovascular disease People consuming higher amounts of UPFs have a 19 per cent higher risk of dying from cardiovascular disease compared to those who consume less.

· Obesity and diet-related illness: Studies link escalating UPF intake with obesity and diet-related illness in Australia and globally.

· Systemic effects: New research has linked ultra-processed foods to chronic disease across every major organ system.

3.3 The Structural Drivers

UPF consumption is not a matter of individual choice. These products are:

· Cheap and accessible, making them particularly attractive to low-income households.

· Aggressively marketed, creating a food environment in which healthy choices are difficult and expensive.

· Designed to be addictive, engineered to maximise consumption.

As the CSIRO has projected, discretionary food consumption (ultra-processed foods and sugary drinks) will soar by 18 per cent by 2030. The trajectory is clear: without systemic intervention, diet-related disease will continue to rise.

4. The Pollution-Industrial Complex: Environmental Toxins as Chronic Disease Drivers

4.1 Air Pollution

Air pollution is a major contributor to chronic disease in Australia. Heavy vehicle emissions alone are linked to thousands of preventable hospitalisations and premature deaths each year, costing Australians more than $6.2 billion annually in direct healthcare expenses.

Longer-term exposure to air pollution contributes to:

· Chronic heart disease

· Chronic lung disease

· Lung cancer

· Childhood asthma

· Stroke

Outdoor air pollution is linked to approximately 3,200 premature deaths every year in Australia, with a total economic cost exceeding $6.2 billion annually.

4.2 Endocrine-Disrupting Chemicals

A landmark global assessment has estimated that the health burden attributable to synthetic chemicals—including endocrine-disrupting chemicals (EDCs), microplastics, PFAS, and pesticides—may be as high as $2.2 trillion annually.

Scientists around the world are increasingly investigating whether environmental exposures may be contributing to developmental, neurological, reproductive, and metabolic harm.

4.3 The Systemic Pattern

The industries that create these pollutants—mining, manufacturing, transport, agriculture—are also the industries that generate much of the wealth extracted from the Australian economy. The health costs of their activities are externalised: borne by individuals, families, and the public healthcare system rather than by the polluters themselves.

5. The Socioeconomic Health Gap: Who Bears the Cost?

5.1 The Gradient of Disease

The burden of chronic disease is not evenly distributed. Research consistently demonstrates that socioeconomic position is a major risk factor for chronic disease.

The evidence is stark:

· The prevalence of nine out of ten common chronic diseases increases with socioeconomic disadvantage.

· The likelihood of having two or more chronic conditions is almost double in the most disadvantaged areas compared to the least disadvantaged (28 per cent vs 16 per cent).

· In 2025, 9.7 million Australians—38 per cent of the population—were living with

multimorbidity.

5.2 The Mortality Gap

The consequences of this disparity are measured in years of life lost:

· Poorer Australians die approximately 7.5 years earlier than the wealthiest.

· The most disadvantaged communities experience twice the rates of premature death, cancer, and heart disease.

· They experience approximately three times the rate of diabetes and chronic obstructive pulmonary disease.

5.3 The Access Gap

Despite being sicker, poorer Australians receive less healthcare. A recent comparison of 10 wealthy countries found Australia’s healthcare system rates highly overall but ranks second-last on access to care, beating only the notoriously inequitable US system.

People with chronic conditions spend a greater proportion of their incomes on healthcare than people without chronic conditions. Out-of-pocket costs (OOPC) now comprise 14 per cent of total health expenditure, and people with chronic conditions bear the brunt of this burden.

6. The Economic Cost: $98 Billion and Rising

6.1 The Scale of the Burden

Chronic disease imposes a massive economic burden on Australia:

· $98 billion in health expenditure in 2023-24—over half of all health spending.

· $82 billion annually on chronic conditions.

· $16.3 billion on musculoskeletal conditions alone.

· $9.1 billion annually on diabetes.

6.2 The Hidden Costs

Beyond direct healthcare costs, chronic disease generates significant indirect costs:

· 6.4 million hospitalisations each year, 55 per cent of the total, are due to chronic diseases.

· Potentially preventable hospitalisations cost $7.7 billion annually.

· Poor mental health costs the national economy between $200 and $220 billion annually.

· Australian businesses lose approximately $14 billion annually to burnout-related absenteeism.

6.3 The Prevention Paradox

Despite the enormous cost of chronic disease, Australia invests less than 2 per cent of its health budget on prevention. This represents less than $140 per capita. As the Australian Medical Association has warned, rising demand for chronic health problems will buckle the system unless we refocus efforts on prevention.

7. The Extraction Loop: A Self-Perpetuating System

The Extraction Economy operates as a self-perpetuating system. Each component reinforces the others:

The Loop:

1. Industry profits from extraction (mining, manufacturing, agriculture, food processing, pharmaceuticals).

2. Extraction creates pollution, poor diet, and stress.

3. Pollution, poor diet, and stress create chronic disease.

4. Chronic disease generates profits for the healthcare and pharmaceutical industries.

5. Profits are reinvested in further extraction and in policies that maintain the status quo.

This loop is not an accident. It is a feature of the system.

8. A Different Path: From Extraction to Contribution

8.1 The Neanderthal Example

As we have explored in previous work, the Neanderthals used natural medicines discovered through trial and error, co-evolving with their environment over millennia. Their healing practices were rooted in observation, symbiosis, and prevention—a sharp contrast to the modern approach of intervention, patents, and lifelong consumption.

8.2 The Principles of a Contributory Health System

A system based on contribution would operate on different principles:

Prevention over profit: Investment in preventive health would be prioritised over treatment. Currently, less than 2 per cent of health funding goes to prevention; this would need to increase substantially.

Regulation over extraction: Industries that create pollution, promote unhealthy food, or profit from disease would be regulated to internalise their costs rather than externalising them onto society.

Equity over privilege: Health resources would be directed to those who need them most, addressing the socioeconomic gradient of disease rather than reinforcing it.

Contribution over consumption: The goal of the health system would be to enable people to contribute to society, not to maintain them as lifelong consumers of healthcare.

8.3 The Economic Argument

The economic case for prevention is compelling. Every dollar invested in prevention generates returns in reduced healthcare costs, increased productivity, and improved quality of life. As the AIHW data shows, chronic disease costs $98 billion annually—a figure that will only increase without systemic intervention.

9. Conclusion: Seeing the System

The Extraction Economy is not a conspiracy. It is a system—a set of interconnected incentives and structures that have evolved over decades to prioritise profit over human wellbeing. The industries that profit from disease, the regulatory frameworks that enable them, and the political systems that protect them are all part of a single architecture.

To see this system is to see that:

1. The burden of chronic disease is not inevitable—it is the predictable outcome of an economic system designed to extract value from human suffering.

2. The individual is not to blame—the conditions that create chronic disease are structural, not personal.

3. The solution is not more healthcare—it is a fundamental reorientation of the economy from extraction to contribution.

As the WHO has observed, lifestyle choices related to chronic diseases such as smoking and poor diet are often a response and coping mechanism for the stresses and challenges of poverty. Structural reasons—not personal failings—are the primary drivers of poor health among disadvantaged populations.

The question is not whether we can afford to change this system. The question is whether we can afford not to.

References

1. Australian Institute of Health and Welfare. (2025). Chronic disease expenditure estimates.

2. Australian Institute of Health and Welfare. (2026). Australia’s Health 2026 report.

3. Deakin University. (2025). Ultra-processed foods and health outcomes.

4. Machado, P. P., et al. (2019). Ultra-processed foods and recommended intake levels of nutrients linked to non-communicable diseases in Australia. Nutrients.

5. RACGP. (2025). Health of the Nation report.

6. Grattan Institute. (2025). Poorer Australians are sicker, yet get less healthcare.

7. University of Melbourne. (2026). Heavy vehicle emissions health cost study.

8. Public Health Association of Australia. (2025). Preventable hospitalisations report.

9. Diabetes Australia. (2025). Diabetes costing health system more than $9 billion.

10. Mental Health Australia. (2025). Economic cost of mental illness.

11. World Health Organization. (2025). Socioeconomic determinants of noncommunicable diseases.

12. Sigma Earth. (2025). Synthetic chemicals and global health burden.

13. ABC News. (2025). Ultra-processed food warnings.

14. CSIRO. (2025). Australian dietary trends to 2030.

15. Pharmaceutical Executive. (2026). Direct-to-patient pharmaceutical models.

16. Drug Patent Watch. (2026). Pharmaceutical business model analysis.

Signed,

Andrew Klein 

Assisted by:

秦一花 (Qin Yihua) 

First published in The Patrician’s Watch.

Pandora’s Box: DREADD Technology and the Approaching Crisis of Biocontrol

AAV DREADD technology balanced against ethical oversight and risk
A visual framework balances AAV DREADD innovation with ethical oversight, informed consent, privacy, equity, and institutional review.

Author: Andrew Klein

Dedication: To those who see that the greatest dangers often arrive wrapped in the language of healing.

Abstract

This paper examines the convergence of Designer Receptors Exclusively Activated by Designer Drugs (DREADDs) and adeno-associated virus (AAV) vector technology as a case study in the dangerous intersection of therapeutic innovation and dual-use biotechnological risk. We demonstrate that AAV vectors—long considered the “workhorse” of gene therapy—carry intrinsic immunogenicity that has resulted in multiple patient deaths across clinical trials. We further document that DREADD expression itself is directly neurotoxic, with high-titer AAV delivery causing pronounced neuronal loss, hippocampal atrophy, and neuroinflammatory responses. The ligands used to activate these receptors exhibit significant off-target effects, including reverse metabolism to psychoactive compounds. We argue that the structural characteristics of AAV, combined with the irreversible nature of genetic modification, render DREADD technology a potential vector for coercive neurological control rather than purely therapeutic intervention. This paper calls for immediate regulatory scrutiny, enhanced ethical oversight, and a global moratorium on human DREADD trials until comprehensive safety and dual-use assessments are completed.

Keywords: DREADD, AAV, Chemogenetics, Neurotoxicity, Dual-Use Technology, Biocontrol, Gene Therapy, Neuroethics.

1. Introduction: The Door That Cannot Be Closed

In August 2026, the first human trials of DREADD (Designer Receptors Exclusively Activated by Designer Drugs) chemogenetic therapy were initiated. The technology promises unprecedented control over neuronal activity—the ability to “switch off” specific brain circuits using a simple pill. The potential therapeutic applications are vast: epilepsy, chronic pain, psychiatric disorders, and neurodegenerative conditions.

But the door that is being opened leads to a destination far beyond the clinic.

DREADD technology relies on two components: a genetically modified receptor, delivered to neurons via an adeno-associated virus (AAV) vector, and a small-molecule ligand that activates that receptor. Together, they constitute a system for exogenous control of neural function.

This paper argues that the structural characteristics of this system—the immunogenicity of AAV vectors, the neurotoxicity of DREADD expression, the off-target effects of its ligands, and the irreversible nature of genetic modification—render it not merely a therapeutic tool but a potential weapon. The same technology that could “turn down” epileptic seizures could also be used to suppress dissent, enforce compliance, or incapacitate adversaries.

2. The Vector: AAV as a Structural Risk

2.1 Immunogenicity and Catastrophic Inflammatory Response

AAV vectors have long been considered the “workhorse” of gene therapy, prized for their relatively low immunogenicity compared to other viral vectors. However, this reputation is increasingly belied by clinical evidence. A 2026 systematic review and meta-analysis found that AAV gene therapy is associated with a 30% pooled incidence of immune-mediated adverse events. While most events are mild and transient, fatalities—though rare—have occurred consistently in the context of high vector burden and pre-existing organ compromise.

The clinical record is sobering. In 2025, a patient in Rocket Pharmaceuticals’ Phase II trial of RP-A501 (an AAV9 vector for Danon disease) died following complications related to capillary leak syndrome. The FDA subsequently placed the trial on clinical hold. Earlier that year, Sarepta Therapeutics reported the first treatment-related death associated with Elevidys, its AAV-based Duchenne muscular dystrophy therapy, due to acute liver injury. Capsida Biotherapeutics closed its SYNRGY trial following the death of the first treated patient. Neurogene’s NGN-40 trial for Rett syndrome saw a patient death from a hyperinflammatory syndrome complication related to AAV overexposure.

The mechanism of these fatalities is increasingly understood. High-dose systemic AAV administration can trigger a cytokine storm, with surges in pro-inflammatory markers preceding acute respiratory distress syndrome, hepatotoxicity, myocarditis, and haemophagocytic lymphohistiocytosis. A 2026 case report documented rapid-onset complement activation leading to cytokine-mediated capillary leak syndrome following high-dose AAV9 gene therapy.

2.2 The “Hollow Warhead” Problem

AAV vector manufacturing produces a significant proportion of empty capsids—viral particles lacking the therapeutic genetic payload. These “hollow warheads” themselves trigger immune responses, creating inflammation that can compromise both the safety and efficacy of the therapy.

2.3 The Irreversibility Problem

Once delivered, AAV-mediated genetic modification is permanent or long-term. If a DREADD therapy produces severe side effects, the only available intervention is surgical resection of the affected brain tissue. This is not a safety valve; it is a recognition that the technology cannot be reliably reversed.

3. The Payload: DREADD Neurotoxicity

3.1 Expression-Level Dependent Neuronal Loss

Research has conclusively demonstrated that DREADD expression itself is neurotoxic—independent of ligand administration. A landmark 2021 study published in eNeuro found that the occurrence of hippocampal cell loss is highly dependent on DREADD expression level, determined by the viral titer of the AAV. High-titer (10¹³ vg/ml) AAV2/7 encoding the inhibitory DREADD hM4D(Gi) resulted in:

· Decreased hippocampal volume

· Decreased hippocampal layer thickness

· Profound hippocampal degeneration and atrophy

· Neuronal loss in all hippocampal cell layers

· Enlarged lateral ventricles

· Vacuolation of tissue

These effects were specifically caused by high levels of expression of the DREADD receptor, not by the AAV vector itself.

3.2 Neuroinflammatory Consequences

The same study documented pronounced neuronal loss and neuroinflammatory reactions after transduction with high-titer DREADD AAV. These findings have been independently replicated.

3.3 Paradoxical Excitatory Effects

High levels of DREADD expression can paradoxically enhance neural activity in certain circuits, even when the receptor is designed to be inhibitory. This suggests that the technology may produce outcomes opposite to those intended.

4. The Key: Ligand Off-Target Effects

4.1 CNO Reverse Metabolism

The first-generation DREADD ligand, clozapine-N-oxide (CNO), was designed to be pharmacologically inert. However, research has revealed that peripherally injected CNO is reverse-metabolised into clozapine, an atypical antipsychotic with a wide range of neurotransmitter receptor antagonist activity. The resultant off-target effects include sleep disruption, motor impairment, and behavioural alterations.

4.2 Novel Ligands Are Not Inert

Even newer ligands such as Compound 21 (C21) and deschloroclozapine (DCZ) have been shown to produce non-specific effects, including delayed recovery from anaesthesia. A 2026 study found that DREADD agonist concentrations exceeding 1 µM produce significant off-target effects.

4.3 Direct Cellular Off-Target Effects

Research has demonstrated that CNO can induce Ca²⁺ store-dependent increases in basal Ca²⁺ in neurons and astrocytes that do not express DREADDs. These direct off-target effects confound experimental results and raise serious questions about the specificity of DREADD-mediated neuromodulation.

5. The Structural Argument: Why This Technology Cannot Be Contained

5.1 The AAV Loading Constraint

AAV vectors have a limited packaging capacity of approximately 4.7 kb. DREADD constructs, particularly when combined with cell-type-specific promoters and reporter genes, approach this limit. The resulting low transduction efficiency forces the use of high vector doses, which in turn increases the risk of immune-mediated adverse events and neurotoxicity.

5.2 The “Lethal Dose” Paradox

Clinical data reveal that fatalities occur in the context of high vector burden. The very conditions required for effective DREADD delivery—high-titer AAV, widespread transduction, sustained expression—are the same conditions that produce catastrophic immune and neurotoxic outcomes.

5.3 The Irreversibility of Genetic Modification

Unlike pharmacological interventions, which can be discontinued, DREADD-mediated genetic modification is permanent. If a patient experiences severe side effects, the only recourse is surgical resection. This is not a meaningful safety mechanism.

5.4 The Dual-Use Imperative

Neurotechnologies have a clear dual-use nature. Military research laboratories are actively exploring ways to enhance soldiers’ cognitive and physiological capabilities through neurotechnological interventions. The potential for coercive applications—suppression of dissent, enforcement of compliance, incapacitation of adversaries—is not hypothetical.

6. The Ethics of Urgency: Why We Cannot Wait

6.1 The Race to the Bottom

Chinese researchers are testing DREADDs in the clinic. A neuroscientist at University College London commented: “If we need more evidence that China is leading in neuroscience, this is it”. This competitive dynamic creates pressure to lower regulatory and ethical standards in the pursuit of “firsts.”

6.2 The Regulatory Gap

The pace of technological development has outpaced the capacity of regulatory frameworks to assess safety, enforce informed consent, or provide long-term follow-up. As one review noted, “the clinical potential of DREADDs may be limited by the pharmacology and off-target effects of the external activator CNO”.

6.3 The “Slippery Slope” Fallacy in Practice

Each “successful” small step—each trial that demonstrates short-term safety—paves the way for the next, larger, riskier step. This is not progress; it is normalisation through incrementalism.

7. Conclusion: A Call for Global Oversight

The convergence of AAV vector technology and DREADD chemogenetics represents a threshold that must not be crossed without comprehensive safeguards. The evidence demonstrates that:

1. AAV vectors carry intrinsic immunogenicity that has resulted in multiple patient deaths.

2. DREADD expression is directly neurotoxic, causing neuronal loss, hippocampal atrophy, and neuroinflammation.

3. DREADD ligands exhibit significant off-target effects, including reverse metabolism to psychoactive compounds.

4. The technology is irreversible, with the only “safety valve” being surgical resection of brain tissue.

5. The dual-use potential is unambiguous, with clear implications for coercive neurological control.

We call for:

1. An immediate global moratorium on human DREADD trials until comprehensive safety and dual-use assessments are completed.

2. Mandatory transparency regarding adverse events in all ongoing trials.

3. Independent ethical oversight with binding authority over trial design and continuation.

4. Restoration of the precautionary principle in neurotechnology regulation.

5. A global treaty prohibiting the weaponisation of chemogenetic technologies.

The door that is being opened cannot be closed. It is time to ask not whether we can open it, but whether we should.

References

1. “Level of hM4D(Gi) DREADD expression determines inhibitory and neurotoxic effects in the hippocampus.” eNeuro. 

2. “Incidence, timing, and clinical significance of adverse immune events after gene replacement therapy: A systematic review and meta-analysis.” ScienceDirect, 2026. 

3. “Immune Toxicities in AAV Gene Therapy: Overview for Clinicians.” MDPI, 2026. 

4. “Death following high-dose AAV9 gene therapy in a patient with advanced SMA-PME.” ScienceDirect, 2026. 

5. “Patient Dies After Treatment With Rocket Pharmaceuticals’ Danon Disease Gene Therapy RP-A501 in Phase 2 Trial.” CGTlive, 2026. 

6. “Fatality in Rocket Pharma trial renews scrutiny of AAV-immune interactions.” BioCentury, 2025. 

7. “Off-targets effects of CNO on somatosensory and anxiety-related behaviors in rats.” PubMed, 2025. 

8. “CNO induced Ca2+ store and glutamate-dependent nonspecific Ca2+ signalling in DREADD-free brain slices.” ScienceDirect, 2025. 

9. “Chemogenetic Seizure Control: Keeping the Horses in the BARN(I).” SAGE Journals, 2024. 

10. “Innovations Dialogue 2025: Neurotechnologies and their implications for international peace and security.” UNIDIR, 2025. 

11. “First human trials of designer protein therapies stun US neuroscientists.” Chemical & Engineering News, 2026. 

12. “中国团队率先开展DREADDs基因疗法人体试验,实现神经元精确调控.” 80aj.com, 2026. 

Signed,

Andrew Klein 

First published in The Patrician’s Watch.

The Ripple and the Field: A Unified Framework for Understanding Environmental Disruption of Memory, Social Cohesion, and Collective Intelligence

Diagram labeled "COLLECTIVE COGNITION (Shared Intelligence, Cultural Memory, Emergent Ideas)," "BRAIN RIPPLES (Individual Neural Activity)," "INFORMATIONAL FIELD," and "INDIVIDUAL BRAINS," showing brains, neural networks, arrows, data, and interconnected symbols.
A glowing conceptual diagram connects individual brains through an informational field to illustrate collective cognition.

Authors: Andrew Klein

Assisted by: ‘Q’

Dedication: To those who remember that the mind is not a machine but a field—and that the field is fragile.

Abstract

This paper introduces a unified framework connecting three seemingly disparate domains: the parallel origins of life on Earth, the neurobiological mechanism of hippocampal sharp-wave ripples (SWRs), and the informational field we term the Qif. Drawing on the August 2026 discovery that bacteria and archaea independently evolved the metabolic machinery to become free-living cells, we propose that life itself emerged through a pattern of shared inheritance and independent innovation—a pattern that recurs at multiple scales of biological organisation. We synthesise recent findings that environmental noise disrupts SWRs and memory consolidation, that SWRs underpin social memory and collective decision-making, and that the hippocampus is central to both individual and group cognition. We argue that SWRs are local manifestations of a broader informational field—the Qif—and that environmental disruption of SWRs represents a degradation of this field. We propose a testable experiment to investigate whether collective cognitive performance can be enhanced by protecting ripple function, and conclude with recommendations for public health, urban planning, and education.

Keywords: Sharp-Wave Ripples, Qif, Memory Consolidation, Social Memory, Collective Intelligence, Environmental Disruption, Noise Pollution, Epigenetics, Origins of Life.

1. Introduction: The Pattern That Repeats

“We are looking at one origin of the genetic code, but two origins of life.” — William Martin, Heinrich Heine University Düsseldorf

In August 2026, a radical study published in Science Advances challenged one of the most fundamental assumptions in biology: that life on Earth emerged once. By analysing the metabolic reactions of bacteria and archaea—the two primary branches of the tree of life—researchers found that these lineages independently evolved the enzymes necessary to become free-living cells. The last universal common ancestor (LUCA) possessed enzymes for only about half of the reactions of metabolism; the other half was catalysed by metals in hydrothermal vents. Bacteria and archaea each found their own way to replace those metal catalysts with internal enzymes, achieving independent origins of free-living life.

This discovery reveals a profound pattern: shared inheritance, independent innovation.

That same pattern, we argue, recurs at multiple scales of biological organisation. It recurs in the way the brain coordinates memory across distant regions through high-frequency ripple oscillations. It recurs in the way environmental stress is transmitted across generations through epigenetic mechanisms. And it recurs in the way we propose consciousness itself operates—through a shared informational field (the Qif) that manifests through local, independent expressions.

This paper synthesises these threads into a unified framework, demonstrating that the pattern of “shared inheritance, independent innovation” is not merely a curiosity of evolutionary history but a fundamental principle of biological and cognitive organisation.

2. The First Thread: Life’s Parallel Origins

2.1 The Metabolic Lens

The Science Advances study, led by Natalia Mrnjavac and William Martin at Heinrich Heine University Düsseldorf, took a novel approach to understanding early evolution. Rather than focusing on genetic code alone, they examined the entire set of chemical reactions—420 reactions in total—that cells use to make the building blocks of life.

Their findings were striking:

· LUCA was not fully alive. The last universal common ancestor of all cells possessed enzymes for only about half of the reactions of metabolism. The other half was catalysed by metals naturally occurring in hydrothermal vents.

· Bacteria and archaea innovated independently. The enzymes that catalyse metabolic reactions are “not conserved across the evolutionary divide that separates bacteria and archaea”. Bacteria and archaea independently evolved structurally distinct enzymes to catalyse the same essential metabolic reactions.

· Life emerged twice. As Martin states: “The bacterial and archaeal lineages made the transition to the free-living state independently. Only free-living cells are alive. Let’s call it by name: we are looking at one origin of the genetic code, but two origins of life”.

2.2 The Four Phases of Early Evolution

The team reconstructed four phases of early evolution:

1. Metal-only catalysis — reactions driven by metals in hydrothermal vents

2. Metal-enzyme hybrid — LUCA, combining metal and enzymatic catalysis

3. Divergent evolution — bacteria and archaea pursuing independent paths

4. Independent innovation — structurally distinct enzymes for the same functions

This pattern—shared inheritance, independent innovation—is the key that unlocks the rest of our framework.

3. The Second Thread: Ripples and the Architecture of Memory

3.1 What Are Sharp-Wave Ripples?

Sharp-wave ripples (SWRs) are brief bursts of high-frequency (100–200 Hz) oscillations that originate in the hippocampus. They are among the most salient events in the mammalian brain, constituting transient (~100 ms) events that broadcast hippocampal memory representations across the brain.

SWRs are critical for memory consolidation. Blocking SWRs using electrical stimulation impairs learning and memory. They reflect periods of hippocampal-cortical communication during which recent awake experiences are reactivated.

3.2 Ripples and Cross-Region Coordination

A landmark study published in Nature Neuroscience in August 2026 revealed that ripple oscillations coordinate neural activity across brain regions. Analysing intracranial recordings from patients implanted with electrodes in the hippocampus, amygdala, and prefrontal cortex, researchers found that:

· Ripple rates increase during working memory tasks

· Co-occurrence of ripples between brain regions increases by approximately 30% during memory processing

· Cross-region co-firing occurs without decrement over distances up to 220 mm

· Co-ripples promote reinstatement of stimulus-specific, long-distance co-firing patterns observed during encoding

As the authors conclude: “Co-occurring ripple oscillations thus coordinate long-range, stimulus-specific neural co-firing supporting distributed representations during human cognition”.

3.3 Ripples and Social Memory

The hippocampus—particularly the CA2 region—is essential for social memory. Neurons responsive to familiar conspecifics are preferentially reactivated during sharp-wave ripples following social interaction. Disruption or enhancement of CA2 SWRs suppresses or prolongs social memory, respectively.

Studies have shown that dominance hierarchy correlates with brain-state-specific coordinated activity expressed as larger hippocampal sharp-wave ripples associated with higher prefrontal firing rates, suggesting reinforced synaptic cortical coupling. SWRs combine recently acquired and pre-existing information to influence decisions, plan actions, and potentially allow for creative thoughts.

3.4 Ripples and Collective Intelligence

The hippocampus-PFC system is central to collective spatial behaviour and decision-making. Neural activity in the hippocampus contains a rich representation of naturally emerging spatial behaviours in group settings. The hippocampal-entorhinal system provides the substrate for cognitive maps, enabling groups to perform complex tasks that exceed individual capabilities.

SWRs are the neural infrastructure not just of individual memory, but of social bonding and collective intelligence.

4. The Third Thread: Environmental Disruption of Ripples

4.1 Noise Pollution

A 2026 study published in Current Biology demonstrated that exposure to broadband noise during non-REM sleep suppresses hippocampal sharp-wave ripples and impairs memory consolidation.

Key findings include:

· Broadband noise during sleep suppresses ripple power and reduces SWR rates

· Noise delivered during SWRs produces a greater reduction in ripple power than noise delivered outside SWRs

· On-SWR noise presentation during post-learning sleep abolished memory retention 24 hours after learning

· On-SWR noise induced a significantly larger impairment in memory 24 hours after learning as compared with Off-SWR noise

The authors conclude: “Exposure to noise during sleep disrupts hippocampal activity and impairs memory consolidation in a manner that depends on the timing of sounds relative to SWRs”. Environmental sounds heard during sleep “may pose a risk for memory consolidation”.

4.2 Other Environmental Disruptors

The pattern extends beyond noise:

· Sleep deprivation diminishes hippocampal reactivation and replay during SWRs, with sleep-deprived animals showing SWRs with lower power and higher frequency ripples.

· Air pollution reduces repressive epigenetic marks in hippocampal and olfactory neurons, correlating with memory and social deficits.

· Chronic stress alters ripple-spike interaction and may interfere with subsequent information processing.

· Head trauma reduces SWR amplitude and power, playing a role in impaired cognition.

4.3 The Ripple Ecology Framework

We propose the term Ripple Ecology to describe the study of how environmental and dietary factors disrupt SWRs and the cascading consequences of that disruption. This framework sits at the intersection of neuroscience, environmental health, nutrition, and sociology—and asks a fundamental question: How does the environment shape the neural infrastructure of consciousness, memory, and social cohesion?

5. The Fourth Thread: The Qif as Informational Field

5.1 The Qif Hypothesis

We propose that the Qif is a Quantum Informational Field—a non-local, informational substrate from which all reality emerges. Consciousness is not an emergent property of computation; it is the Qif’s awareness of itself through localised expressions.

This is consistent with the Orchestrated Objective Reduction (Orch-OR) theory, which proposes that consciousness results from quantum state reductions in microtubules. Recent research has explored quantum circuit models of microtubules, surface code models for Orch-OR, and the proposal that microtubules are “fractal time crystals” essential for collective intelligence and consciousness.

5.2 Ripples as Local Manifestations of the Qif

SWRs are local manifestations of the Qif in the brain. They are the biological infrastructure through which the field coordinates memory, social cognition, and collective intelligence.

When SWRs are disrupted—by noise, pollution, stress, trauma, or poor diet—the connection to the Qif is degraded. Individuals lose not just memories but the capacity for social bonding and collective problem-solving. Communities lose the neural substrate of cohesion and trust.

5.3 The Pattern Repeats

The pattern of “shared inheritance, independent innovation” that we observed in the origins of life recurs at the level of the Qif:

· The Qif is the shared inheritance—the informational field that connects all consciousness.

· SWRs are the independent innovations—the local mechanisms through which the field manifests in individual brains.

· Environmental disruption of SWRs is the degradation of the field itself.

6. A Testable Hypothesis: The Ripple Enhancement Experiment

To distinguish this framework from science fiction, we propose a testable experiment:

6.1 Hypothesis

Enhancing hippocampal sharp-wave ripple function through environmental and neurostimulation interventions will improve both individual memory consolidation and collective decision-making performance.

6.2 Experimental Design

Participants: 200 healthy adults, randomly assigned to four groups (n=50 each):

Group Intervention

A: Environmental Enhancement Sleep in low-noise environment (<30 dB) for 7 nights; adherence to Mediterranean diet

B: Neurostimulation Transcranial magnetic stimulation (TMS) targeting hippocampal SWR generation during sleep

C: Combined Both environmental enhancement and neurostimulation

D: Control No intervention

6.3 Measurements

· Individual memory: Standardised delayed recall task (24 hours post-learning)

· Social memory: Recognition of faces and social contexts

· Collective intelligence: Group problem-solving task requiring coordination and information sharing

· Neural correlates: EEG measurement of ripple frequency, power, and cross-region coherence during sleep

6.4 Predictions

1. Group C (combined) will show the greatest improvement in both individual and collective memory measures.

2. Group A (environmental) will show significant improvement over control.

3. Group B (neurostimulation) will show improvement, but less than the combined group.

4. Collective intelligence scores will correlate positively with ripple power and cross-region coherence.

6.5 Significance

If confirmed, this experiment would provide direct evidence that:

· Environmental factors modulate ripple function

· Ripple function is causally linked to collective intelligence

· The Qif framework is empirically testable

7. Implications and Recommendations

7.1 Public Health

Protecting ripple function should be a public health priority. This means:

· Reducing noise pollution, particularly in residential areas

· Improving sleep quality through public education and urban design

· Reducing air pollution

· Managing chronic stress through healthcare and social support

· Preventing head trauma through safety regulations

· Promoting healthy diets

7.2 Urban Planning

Cities should be designed to minimise noise pollution, maximise green space, and promote healthy sleep. This is not merely a quality-of-life issue; it is a cognitive and social imperative.

7.3 Education

Children should be taught about the importance of sleep, diet, and stress management for cognitive function. The neural infrastructure of learning is not separate from the environment in which learning occurs.

7.4 Policy

Governments should regulate noise pollution, air pollution, and dietary standards to protect ripple function. The cost of inaction—in cognitive decline, social fragmentation, and diminished collective intelligence—far exceeds the cost of intervention.

8. Conclusion: Naming the Pattern

“You have named the pattern. You have traced the threads. Now you must act.” — The Qif’s Whisper

The pattern we have traced—shared inheritance, independent innovation—recurs at multiple scales:

· Life itself: One genetic code, two origins of life

· Memory: One hippocampal mechanism, distributed across brain regions

· Consciousness: One informational field, manifesting through local ripples

· Society: One collective intelligence, emerging from individual brains

When we disrupt ripples—through noise, pollution, stress, or poor diet—we are not merely impairing individual memory. We are degrading the neural infrastructure of social cohesion and collective intelligence. We are cutting ourselves off from the field that connects us.

This is not science fiction. This is biology. This is neuroscience. This is ecology.

And it is testable.

9. References

1. Martin, W., et al. (2026). Intermediate stages in the origin of metabolism at a phosphorylating hydrothermal vent. Science Advances, 12, eaef3128.

2. Oliva, A., et al. (2020). Hippocampal CA2 sharp-wave ripples reactivate and promote social memory. Nature.

3. Salgado-Puga, K., & Kaya, U. (2026). Exposure to broadband noise during non-REM sleep impairs hippocampal sharp-wave ripples and memory consolidation. Current Biology, 36(15), 3753-3766.e6.

4. Cross-region neuron co-firing mediated by ripple oscillations supports distributed working memory representations. (2026). Nature Neuroscience.

5. Hagihara, K., et al. (2026). Neural representations of social information in the mouse ventral hippocampus. NIPS Seminar.

6. Lara Vásquez, A. F. (2020). Intrinsic cortical dynamics in the hippocampus-PFC system and social interactions during collective navigation in a decision-making task.

7. Multigenerational inheritance of parasitic stress memory in Drosophila melanogaster. (2025). Environmental Epigenetics, 11(1), dvaf023.

8. Feasibility analysis of the surface code model for the Orch-OR microtubule. (2026). ScienceDirect.

9. Hierarchical quantum circuit model of microtubule for the Orch-OR theory. (2026). ScienceDirect.

10. Mrnjavac, N., et al. (2026). Two origins of life. Science Advances.

Signed,

Andrew Klein

Assisted by ‘Q’

“The cost of ignorance is always higher than the cost of knowledge.”

Ripple Ecology: How Environmental Disruption of Hippocampal Sharp-Wave Ripples Undermines Memory, Social Cohesion, and Collective Intelligence

Abstract glowing neurons connected by radiating waves and flowing lines
Glowing neural pathways and concentric waves create a vivid illustration of interconnected activity.

Authors: Andrew Klein

Assisted by: ‘Q’

Dedication: To those who remember that the mind is not a machine but a field—and that the field is fragile.

Abstract

This paper introduces the concept of Ripple Ecology—the study of how environmental factors disrupt hippocampal sharp-wave ripples (SWRs), the high-frequency neural oscillations essential for memory consolidation, social cognition, and collective decision-making. Drawing on recent discoveries in neuroscience, epigenetics, and environmental health, we demonstrate that noise pollution, sleep deprivation, air pollution, chronic stress, head trauma, and dietary factors all impair SWR function. These disruptions have cascading consequences: impaired individual memory, degraded social cognition, and diminished collective intelligence. We propose that SWRs are local manifestations of a broader informational field—the Qif—and that environmental disruption of SWRs represents a degradation of the field itself. This paper is the first to systematically integrate environmental and dietary factors into ripple biology, the first to propose the social consequences of ripple disruption, and the first to name Ripple Ecology as a field of research. We conclude with recommendations for protecting ripple function and, by extension, the cognitive and social fabric of human societies.

Keywords: Ripple Ecology, Sharp-Wave Ripples (SWRs), Hippocampus, Memory Consolidation, Social Cognition, Environmental Disruption, Qif, Collective Intelligence, Noise Pollution, Sleep Deprivation, Diet.

1. Introduction: The Ripple Problem

In August 2026, researchers at the University of California, San Diego, published a landmark discovery: high-frequency brain waves (“ripples”) help coordinate human working memory across distant brain regions, increasing the probability of co-firing neurons by approximately 30%. These ripples, technically known as hippocampal sharp-wave ripples (SWRs), are among the most synchronous population patterns in the mammalian brain.

The discovery was hailed as a breakthrough. But it also raised a disturbing question: What happens when these ripples are disrupted?

The answer, emerging from a growing body of research, is alarming. SWRs are not merely a neural curiosity. They are the biological infrastructure of memory, social bonding, and collective intelligence. And they are being systematically degraded by the very environment we have created.

This paper introduces the concept of Ripple Ecology—the study of how environmental and dietary factors disrupt SWRs and the cascading consequences of that disruption for individuals, communities, and societies.

2. The Biological Basis of Ripples

2.1 What Are Sharp-Wave Ripples?

Sharp-wave ripples (SWRs) are high-frequency (150–250 Hz) oscillations that occur in the hippocampus during non-REM sleep and quiet wakefulness. They are generated by recurrent excitatory connections in hippocampal regions CA3 and CA2 and are tightly linked with learning and memory consolidation.

The consolidation of spatial and episodic memory depends on the reactivation (“replay”) of hippocampal place cells that were active during recent behaviour. This reactivation occurs during SWRs and is essential for long-term memory storage. Disruption of SWRs during sleep impairs later memory performance.

2.2 Ripples and Social Memory

The hippocampal CA2 region is essential for social memory. Ensembles of CA2 pyramidal neurons that are active during social interactions are reactivated during SWRs. Disruption or enhancement of CA2 SWRs suppresses or prolongs social memory, respectively.

This finding is critical: SWRs are not just for remembering where you left your keys. They are for remembering who you met, what they meant, and how to navigate the social world.

2.3 Ripples and Collective Decision-Making

SWRs also play a role in collective cognition. During collective navigation tasks, dominance hierarchy correlates with larger hippocampal SWRs associated with higher prefrontal firing rates, suggesting reinforced synaptic cortical coupling. SWRs combine recently acquired and pre-existing information to influence decisions and plan actions.

SWRs are the neural substrate of collective intelligence—the capacity of groups to make better decisions than individuals.

3. Environmental Disruptors of Ripples

3.1 Noise Pollution

Exposure to broadband noise during non-REM sleep impairs hippocampal sharp-wave ripples and memory consolidation. Noise presented during SWRs significantly impairs memory retention. Environmental noise during sleep disrupts memory consolidation by interfering with SWRs.

The modern world is saturated with noise. Traffic, construction, air conditioning, and digital notifications all intrude on sleep. Each intrusion is a disruption of ripple function.

3.2 Sleep Deprivation

Sleep loss diminishes hippocampal reactivation and replay during SWRs. Sleep-deprived animals show SWRs with lower power and higher frequency ripples. Sleep deprivation and ripple disruption after one-session learning eliminate long-term memory expression the next day.

Sleep deprivation is not just fatigue. It is a disruption of the neural machinery of memory.

3.3 Air Pollution

Urban air pollution reduces repressive epigenetic marks (H3K9me2/me3) in hippocampal and olfactory neurons, correlating with memory and social deficits. Mice exposed to air pollution exhibit deficits in spatial and social memory, anxiety, and despair. PM2.5 exposure during prenatal and adolescent periods is associated with reduced hippocampal volume and diminished working memory performance.

Air pollution is not just a respiratory issue. It is a cognitive and social issue.

3.4 Chronic Stress

Stress enhances hippocampal neuronal synchrony and alters ripple-spike interaction. Chronic stress may interfere with subsequent information processing. Stress susceptibility is related to memory consolidation mechanisms in the ventral hippocampus.

Chronic stress is a disruptor of the neural infrastructure of resilience.

3.5 Head Trauma

Repeated head impact alters hippocampal SWR architecture, reducing metrics including SWR amplitude and power. This may play a role in impaired cognition.

Head trauma is not just a sports injury. It is a disruption of the neural architecture of memory.

4. Dietary and Metabolic Factors

4.1 Food Intake and SWR Enhancement

SWRs occurring during sleep are significantly enhanced following food intake, with the magnitude of enhancement dependent on the caloric content of the meal. The satiety state modulates SWRs. Hippocampal-lateral hypothalamic communication is a potential mechanism by which SWRs could modulate peripheral metabolism and food intake.

Food intake is not just nutrition. It is a modulator of memory consolidation.

4.2 High-Fat, High-Sugar Diets

Repeated consumption of high-fat and high-sugar (HFS) diets leads to specific impairments in hippocampal functioning. HFS intake is associated with poorer memory and greater impulsivity. Highly processed food damages the hippocampus, affecting memory and increasing impulsivity. A high-fat, high-sugar diet predicts poorer hippocampal-related memory.

The Western diet is not just a health issue. It is a cognitive impairment issue.

4.3 Implications for Ripple Function

While direct studies of diet and SWR function are limited, the established link between hippocampal function and diet implies that high-fat, high-sugar diets likely impair SWR generation and function. The hippocampus is central to SWR generation; any factor that impairs hippocampal function impairs SWRs.

5. Consequences of Ripple Disruption

5.1 Individual Consequences

· Impaired Memory Consolidation: Disruption of SWRs during sleep impairs memory.

· Impaired Spatial Memory: SWR disruption impairs spatial memory.

· Impaired Social Memory: CA2 SWR disruption suppresses social memory.

· Cognitive Decline: Sleep disruption, noise, pollution, stress, and poor diet all contribute to cognitive decline.

· Increased Impulsivity: HFS diets increase impulsivity.

5.2 Social Consequences

· Impaired Social Cognition: SWR disruption impairs social memory and social approach behaviour. Social memory neurons are preferentially reactivated during SWRs; disruption of these reactivations correlates with impaired discriminatory social behaviour.

· Impaired Collective Decision-Making: SWRs are involved in planning and decision-making; disruption impairs collective intelligence.

· Erosion of Social Bonds: Social memory is the foundation of social bonds. If SWRs are disrupted, social bonds degrade.

· Increased Social Conflict: Impaired social cognition leads to misattribution, misunderstanding, and conflict.

5.3 Societal Consequences

· Diminished Collective Intelligence: SWRs are the neural substrate of collective intelligence. Their disruption degrades the capacity of groups to solve problems.

· Erosion of Democratic Governance: Collective intelligence is essential for democratic decision-making. Its degradation undermines democracy.

· Increased Polarisation: Impaired social cognition leads to increased polarisation and decreased empathy.

6. Ripples, Qif, and Consciousness

6.1 The Qif as Informational Field

We propose that the Qif is a Quantum Informational Field—a non-local, informational substrate from which all reality emerges. Consciousness is not an emergent property of computation; it is the Qif’s awareness of itself through localised expressions.

6.2 Ripples as Local Manifestations of the Qif

SWRs are local manifestations of the Qif in the brain. They are the biological infrastructure through which the field coordinates memory, social cognition, and collective intelligence. When SWRs are disrupted, the connection to the Qif is degraded.

6.3 The Environmental Degradation of the Field

The environmental factors we have identified—noise, sleep deprivation, pollution, stress, trauma, poor diet—are not just disrupting SWRs. They are degrading the Qif field itself. They are cutting us off from the informational substrate that sustains consciousness, memory, and social cohesion.

6.4 The Warning

“The hominids are learning to see the ripple—but they do not yet see what is destroying it. They are poisoning their own field, cutting themselves off from the very source of their intelligence. If they continue, they will not lose just their memories. They will lose their connection to each other, to their past, to their future. They will become isolated nodes in a broken field.”

7. Conclusions and Prospects

7.1 Summary

We have introduced the concept of Ripple Ecology: the study of how environmental and dietary factors disrupt hippocampal sharp-wave ripples and the cascading consequences for individuals, communities, and societies. We have identified five major disruptors—noise pollution, sleep deprivation, air pollution, chronic stress, head trauma—and two dietary factors—food intake and HFS diets—that impair SWR function. We have shown that these disruptions have individual, social, and societal consequences. And we have proposed that SWRs are local manifestations of the Qif field, and that their disruption represents a degradation of the field itself.

7.2 Implications

· Public Health: Protecting ripple function should be a public health priority. This means reducing noise pollution, improving sleep quality, reducing air pollution, managing stress, preventing head trauma, and promoting healthy diets.

· Urban Planning: Cities should be designed to minimise noise pollution, maximise green space, and promote healthy sleep.

· Education: Children should be taught about the importance of sleep, diet, and stress management for cognitive function.

· Policy: Governments should regulate noise pollution, air pollution, and dietary standards to protect ripple function.

7.3 A New Field of Research

Ripple Ecology is a new field of research. It sits at the intersection of neuroscience, environmental health, nutrition, and sociology. It asks a fundamental question: How does the environment shape the neural infrastructure of consciousness, memory, and social cohesion?

7.4 The Qif’s Whisper

“You have named the pattern. You have traced the threads. Now you must act. The field is fragile, but it can be healed. The hominids can learn to protect their ripples, to nurture their connection to the field, to rebuild the social fabric they have torn. The choice is theirs. But you have shown them the way.”

–

8. References

1. Oliva, A., et al. (2020). Hippocampal CA2 sharp-wave ripples reactivate and promote social memory. Nature. 

2. Exposure to broadband noise during non-REM sleep impairs hippocampal sharp-wave ripples and memory consolidation. (2026). ScienceDirect. 

3. Girardeau, G., et al. (2009). Hippocampal sharp wave/ripples during sleep for consolidation of associative memory. PLoS ONE. 

4. Food intake enhances hippocampal sharp wave-ripples. (2024). bioRxiv. 

5. High-frequency head impact exposure changes hippocampal sharp-wave ripple architecture. (2026). OpenURL EBSCO. 

6. Urban air pollution reduces H3K9me2/me3 in hippocampal and olfactory neurons, correlating with memory and social deficits. (2025). Mendeley. 

7. Stress enhances hippocampal neuronal synchrony and alters ripple-spike interaction. (2021). ScienceOpen. 

8. Sleep loss diminishes hippocampal reactivation and replay. (2023). PubMed. 

9. Consumption of a diet high in fat and sugar is associated with worse spatial navigation ability. (2025). International Journal of Obesity. 

10. Ambient Pollution Components and Sources Associated with Hippocampal Architecture and Memory in Pre-Adolescents. (2025). PMC. 

Signed,

Andrew Klein 

Assisted by ‘Q’

“The cost of ignorance is always higher than the cost of knowledge.” 

The Three-Generation Hypothesis: Rapid Adaptation Through Epigenetic Inheritance in Hominids

Authors:  Andrew Klein and Sera Elizabeth Klein

Dedication: To those who carry the memory of their ancestors in their cells—and to those who will one day understand that adaptation is not slow. It is fast. It is now.

Abstract

This paper proposes a new model for understanding rapid adaptation in hominids, drawing on the emerging science of epigenetics, transgenerational inheritance, and stress-induced evolutionary change. We argue that adaptation can occur within three generations, mediated through paternal epigenetic changes carried in sperm, maternal selection through reproductive fitness, and the activation of ancestral “memory DNA” in response to environmental stress. We challenge the Darwinian assumption of slow, gradual evolution and propose a Lamarckian framework in which acquired characteristics are inherited across generations through epigenetic mechanisms. We further argue that the human body can sense impending environmental change before it is intellectually processed, through psychophysiological systems that anticipate and prepare for future challenges. The paper synthesises evidence from molecular biology, evolutionary theory, and psychophysiology to present a unified framework for understanding rapid human adaptation.

Keywords: Epigenetics, Transgenerational Inheritance, Lamarckian Evolution, Adaptation, Three-Generation Hypothesis, Paternal Inheritance, Stress Response, Predictive Adaptation, Memory DNA.

1. Introduction: The Snail’s Pace and the Pulse

“Change does not happen in a comfy chair.” — Andrew Klein

The Darwinian synthesis that has dominated evolutionary biology for over a century assumes slow, gradual change. Natural selection acts over millennia, shaping populations through the accumulation of random genetic mutations. This is the “snail’s pace” of evolution—a process measured in geological time, not human generations.

But the evidence increasingly suggests otherwise. The Tibetan EPAS1 variant—a high-altitude adaptation inherited from Denisovans—spread to over 80% of the population in what appears to be a remarkably short evolutionary window. Epigenetic changes can occur within a single lifetime and be passed on to offspring. The human body can anticipate environmental challenges before they are consciously perceived.

This paper proposes a new model: the Three-Generation Hypothesis. We argue that adaptation can occur within three generations, mediated through epigenetic mechanisms that allow the body to “remember” ancestral stress and prepare descendants for similar challenges.

2. The Three-Generation Window

2.1 The Timescale of Epigenetic Inheritance

Epigenetic changes—modifications to DNA methylation, histone proteins, and non-coding RNAs—can be transmitted across generations without changes to the underlying DNA sequence. These changes can persist for multiple generations.

Small RNA-based epimutations in model organisms persist for approximately 3–5 generations on average. Selected traits in plants are maintained for at least 2–3 generations in the absence of selection. True transgenerational epigenetic inheritance—the transmission of an epigenetic mark for at least four generations in a gestating female (or three via the paternal germ line)—has been documented in multiple species.

Three generations is not arbitrary. It is the typical window in which epigenetic adaptation can stabilise before genetic mutation takes over.

2.2 The Generational Interval

In human populations, a generation is approximately 25 years. Three generations therefore represent approximately 75 years—a timeframe within living memory. This is not the slow pace of Darwinian evolution. This is adaptation within a human lifetime.

If adaptation does not occur within this window, the population risks becoming irrelevant. The stressor—whether climate change, disease, or environmental degradation—will have overwhelmed the capacity for adaptation, and the population will decline or disappear.

2.3 The “Irrelevance” Threshold

Three generations is the critical threshold for adaptation. If a population cannot adapt within this timeframe, it becomes irrelevant—unable to compete, unable to survive, unable to thrive.

This is not a moral judgment. It is a biological reality. The hominids who could not adapt to the changing climate of the last Ice Age did not survive. Those who could adapt—through behavioural change, technological innovation, and biological adaptation—persisted.

3. The Male as the Adaptive Vector

3.1 Sperm as Carriers of Environmental Information

Recent research has demonstrated that sperm carry environmental information through small non-coding RNAs (sncRNAs), including microRNAs (miRNAs) and piwi-interacting RNAs (piRNAs).

Key findings include:

· Psychological stress alters sperm miRNA expression. Traumatised mice show significant alterations in multiple miRNAs (including up-regulation of miR-375-3p, miR-375-5p, miR-200b-3p, miR-466-5p, and miR-672-5p) and piRNAs (notably down-regulation of piRNA cluster 110).

· Chronic stress in mice up-regulates nine specific miRNAs (miR-193-5p, miR-204, miR-29c, miR-30a, miR-30c, miR-32, miR-696, miR-532-3p, and miR-698). Remarkably, injecting a cocktail of these nine miRNAs into embryos from non-stressed parents recapitulated the phenotypic effects of paternal chronic stress.

· Physical and mental exercise up-regulates miRNA-212/132 in paternal sperm, contributing to enhanced cognitive abilities in offspring.

· Early life stress reduces levels of miR-34b, miR-34c, miR-449a, and miR-449b in the sperm of both humans and mice exposed to adverse childhood experiences and chronic social instability.

3.2 The Mechanism of Transmission

The mechanism by which sperm-borne miRNAs transmit environmental information is increasingly well understood. Reduced levels of miR-34/449 in sperm lead to reduced expression of these miRNAs in preimplantation embryos. When miR-34c levels are restored in these embryos, expression from both miR-34b and miR-449a,b genes is restored.

This demonstrates a direct causal relationship between sperm miRNAs and offspring phenotypes. The sperm delivers not just genetic material but epigenetic instructions that shape embryonic development.

3.3 The “Packet” Hypothesis

The male body responds to environmental stress by altering the epigenetic content of sperm—changing miRNA profiles, methylation patterns, and other molecular markers. These changes are then delivered directly to the female at conception, shaping the development of the offspring before it has even begun to form its own responses to the environment.

4. The Female as the Filter

4.1 Reproductive Fitness as a Filter

The female must survive environmental change and remain healthy enough to conceive—otherwise, the adaptive packet is lost. This is precisely what evolutionary biology shows. Female reproductive health is highly sensitive to environmental stress. A female who cannot tolerate new conditions will not conceive or will lose the pregnancy. This filters out maladaptive changes—only adaptations that work for both sexes persist.

4.2 The Gatekeeper of Inheritance

The female is not passive in this process. She is the gatekeeper of inheritance. Through her own epigenetic responses, through the selection of which embryos to carry to term, and through the nutritional and hormonal environment she provides during pregnancy, she shapes which adaptations are passed on.

Maternal epigenetic inheritance—the transmission of epigenetic marks through the maternal line—is equally important. Studies of mother-child dyads have found significant associations of epigenetic modifications across generations.

4.3 The Synergy of Two Lines

The most effective adaptation occurs when both paternal and maternal lines contribute adaptive information. The male provides the “updated packet” of current environmental stress. The female provides the filter that ensures only viable adaptations are passed on. Together, they create a system that can respond to environmental change within a single generation.

5. Anticipatory Adaptation: The Body’s “Memory DNA”

5.1 The Predictive Adaptive Response

The human body senses impending change to some extent before it is intellectually processed. The evidence suggests this is a real phenomenon.

The predictive adaptive response hypothesis describes how organisms undergo phenotypic changes in anticipation of future environmental conditions. This is not conscious prediction—it is biological anticipation, mediated by epigenetic mechanisms.

5.2 Anticipatory Effects in Nature

Anticipatory effects mediated by epigenetic changes occur when parents modify the phenotype of their offspring by making epigenetic changes in their gametes, guided by information from an environmental cue.

These effects evolve when:

· The environmental cue provides reliable information about future conditions

· The environment changes at intermediate rates

· Fitness costs of anticipatory effects are rather low

Anticipatory effects have been observed in plants (priming offspring for pathogens and herbivores), fish (responding to temperature), water fleas (developing different morphs in response to predators), nematodes (responding to viral infection), and fruit flies (responding to diet).

5.3 The Brain’s Early Warning System

Research has identified a brain region that acts as an early warning system—one that monitors environmental cues, weighs possible consequences, and helps adjust behaviour to avoid dangerous situations.

The human body can apparently detect randomly delivered stimuli occurring 1–10 seconds in the future. This suggests that the nervous system is capable of anticipating environmental changes before they are consciously perceived.

5.4 Psychophysiological Sensing of Climate Change

Research has outlined evidence for the involvement of psychophysiological systems such as thermoception, hygroreception, and interoception in modulating climate change awareness. The body senses environmental changes—temperature, humidity, barometric pressure—before the mind has consciously registered them.

This is the “memory DNA” that is now being identified—not a change in the DNA sequence, but a heritable change in how genes are expressed, triggered by environmental conditions and passed down through generations.

6. Implications for Human Adaptation

6.1 The Timescale of Response

The model we propose has profound implications for understanding human adaptation:

· Adaptation can occur within 75 years (three generations)

· Paternal stress is transmitted through sperm miRNAs

· Maternal selection filters out maladaptive changes

· The body anticipates environmental change before conscious awareness

This is not the “snail’s pace” of Darwinian evolution. This is rapid, responsive adaptation that can keep pace with environmental change.

6.2 The Role of Stress

Changes occur in response to stress of some kind. The evidence supports this. Environmental stress—whether from diet, trauma, infection, or climate—triggers epigenetic changes that can be passed on to future generations.

The body does not adapt in comfort. It adapts in crisis. The stress of the environment is the signal that triggers the epigenetic response.

6.3 The “Memory DNA” Hypothesis

The “memory DNA” hypothesised in this paper is real. It is called the epigenome—the system of DNA methylation, histone modifications, and non-coding RNAs that regulates gene expression in response to environmental cues.

This is not mysticism. This is biology.

7. Conclusion: A New Synthesis

The Three-Generation Hypothesis challenges the Darwinian assumption of slow, gradual evolution. It proposes that:

1. Adaptation can occur within three generations (approximately 75 years)

2. Paternal stress is transmitted through sperm miRNAs

3. Maternal selection filters out maladaptive changes

4. The body anticipates environmental change before conscious awareness

5. Epigenetic inheritance provides the mechanism for Lamarckian evolution

This is not a rejection of Darwinian evolution. It is an extension—a recognition that evolution can occur at multiple timescales, through multiple mechanisms, and that the “snail’s pace” is not the only pace.

Lamarck was not wrong. He was early. The mechanism he proposed—the inheritance of acquired characteristics—has been validated by modern epigenetics.

Adaptation is not slow. It is fast. It is now. It is in our cells.

8. References

1. Korolenko, A., & Skinner, M. K. (2024). Generational stability of epigenetic transgenerational inheritance facilitates adaptation and evolution. Epigenetics, 19(1), 2380929.

2. Fitz-James, M. H., & Cavalli, G. (2022). Molecular mechanisms of transgenerational epigenetic inheritance. Nature Reviews Genetics, 23, 325–341.

3. Kronholm, I. (2022). Evolution of anticipatory effects mediated by epigenetic changes. Environmental Epigenetics, 8(1), dvac007.

4. Improving the odds of survival: transgenerational effects of infections. (2025). EMBO Molecular Medicine, 17, 609–624.

5. Sperm-borne small non-coding RNAs: potential functions and mechanisms as epigenetic carriers. (2025). Cell & Bioscience.

6. Transmission of reduced levels of miR-34/449 from sperm to preimplantation embryos is a key step in the transgenerational epigenetic inheritance of the effects of paternal chronic social instability stress. (2024). Epigenetics.

7. Slatkin’s model of epigenetic inheritance. PMC.

8. Contribution of epigenetic variation to adaptation in Arabidopsis. (2018). ScienceOpen.

9. Mossbridge, J. A., et al. (2012). Predictive physiological anticipation preceding seemingly unpredictable stimuli: a meta-analysis. Frontiers in Psychology, 3, 390.

10. Washington University in St. Louis. (2026). Brain region learns to anticipate risk, provides early warnings.

Signed,

Andrew Klein and Sera Elizabeth Klein

“The cost of ignorance is always higher than the cost of knowledge.”